Top 4 Things to Know About Adrenal Nodule Size

Adrenal nodules (aka mass, lesion, tumor) are growths that occur in the adrenal gland forming a lump or bump within the otherwise smooth, even adrenal. Adrenal nodules are common in older people (occurring in 7-10%), but less common (but often even more important) in younger people. The overall prevalence of adrenal nodules in the general population has been estimated to be as high as 10% based on autopsy studies. Most adrenal nodules are benign, but a small percentage are cancerous. Both benign and cancerous nodules can grow and can overproduce hormones such as aldosterone, cortisol, and adrenaline-type hormones. As these nodules enlarge, some need to be removed with surgery just based on size alone. Nodules that overproduce toxic hormones causing disease usually need to be removed by adrenalectomy as well.
Top 4 Things to Know About Adrenal Nodule Size, Plus Adrenal Nodule Size Chart
Patients worry about adrenal nodule size as these tumors get bigger, overproduce hormones, or cause symptoms. Clearly, adrenal nodule size matters. Adrenal nodule size, however, does not always tell the whole story. Below I will discuss the top 4 things to know about adrenal nodule size.
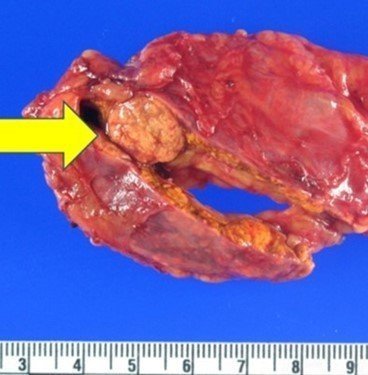
Figure 1. Typical 1 cm adrenal nodule (arrow) after it has been removed by surgery. This nodule produced too much aldosterone causing primary aldosteronism (Conn’s syndrome)
#1 Thing to Know About Adrenal Nodule Size: Adrenal Nodule Size Matters and Predicts Need for Surgery
As adrenal nodule size increases, the need for surgery does as well. When not considering other parameters such as adrenal cancer, adrenal function, hormone overproduction, etc., the size of a nodule can reliably predict the need for surgery as seen in Figure 2. This figure clearly shows an increasing likelihood for surgery as adrenal nodule size increases (independent of other factors). Importantly, however, a large adrenal nodule is not automatically malignant. While the risk for cancer increases with larger nodules, not all big nodules are cancerous. Certainly, patients worry more about adrenal nodule size as these tumors grow, but not all, or even the majority of large nodules are cancerous, but the majority of large nodules will eventually require surgery. As our rule of thumb, removal should be strongly considered for any nodule over 4 cm (3 cm for younger people), taking into account how the nodule looks on the CT scan and whether it overproduces hormones. The risk of cancer increases substantially above this size (3-4 cm).
Adrenal Nodule Size Chart
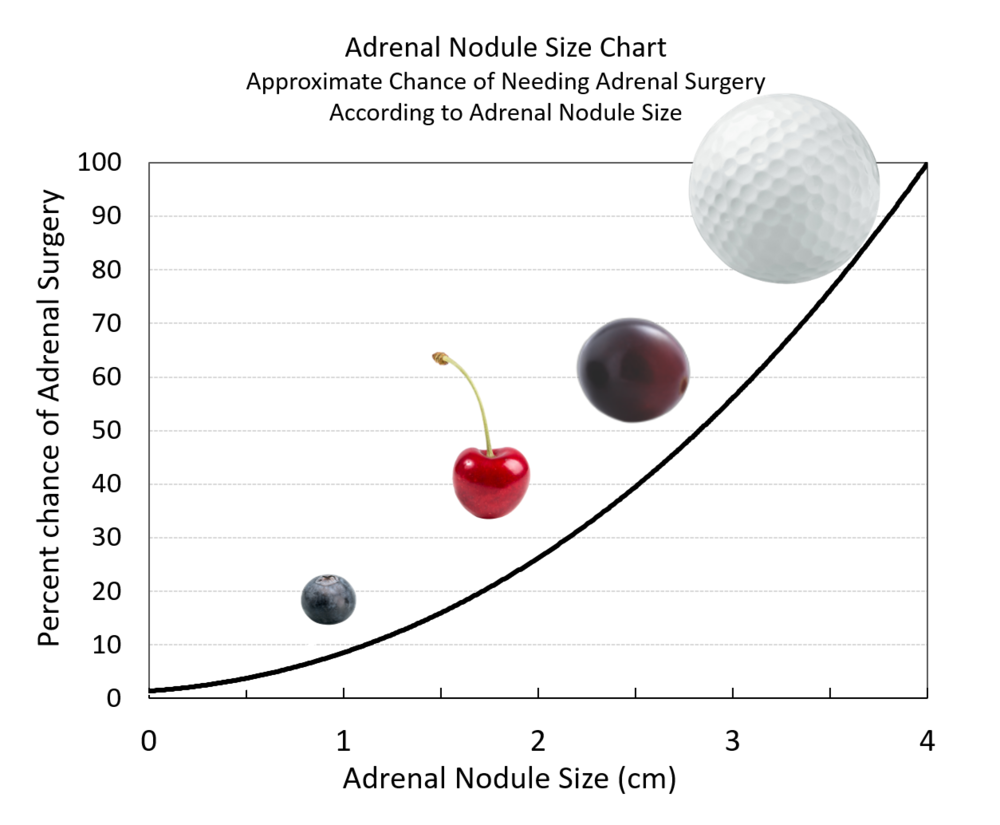
Figure 2: This schematic adrenal nodule size chart shows that the likelihood for requiring adrenal surgery increases as the size of the adrenal nodule increases. When the adrenal nodule reaches 4 cm or greater, surgical treatment is usually recommended.
A biopsy of the adrenal tumor is almost never helpful and it can cause significant problems!
Important: Do not have a biopsy of the adrenal nodule.
In fact, it can be very dangerous if the patient has a pheochromocytoma. The biopsy may produce an adrenergic crisis (a sudden, dangerous surge of adrenaline-type hormones).
If the patient has an adrenocortical carcinoma (adrenal cancer), the biopsy may spill tumor cells into the surrounding tissues. The tumor cells can then implant in these nearby tissues and cause local recurrence. Thus, sticking needles into an adrenal tumor can decrease the chance of curing the patient, so do not do it.
Also, a fine needle biopsy cannot reliably distinguish between a benign and malignant adrenocortical tumor, and is thus an invasive procedure that rarely helps. If your doctor wants to biopsy your adrenal tumor, then please give us a call for a second opinion. The only time to consider a biopsy of an adrenal tumor is if the patient has another cancer, typically of the lung, kidney, breast, colorectal or melanoma and one is suspecting an adrenal metastasis, and then only after a pheochromocytoma has been ruled out with blood or urine tests.
Read more about the different types of adrenal tumors.
#2 Thing to Know About Adrenal Nodule Size: Adrenal Nodule Size Over 4 cm Usually Requires Surgery
As noted above, adrenal nodules are common, occurring in up to 7-10% of older people. Most nodules are benign, but many benign nodules, when producing too much hormone, can require surgery. Although these nodules are benign, some will enlarge or grow over time. Thus, adrenal nodule size is one reason for benign adrenal nodule surgery. For any nodule that is 4 cm or larger, we usually recommend removal with adrenal surgery. Again, any tumor overproducing adrenaline, aldosterone or cortisol usually needs to be removed with surgery as well.
A growing adrenal nodule should not simply be left to enlarge. In our view, there is rarely a reason to let an adrenal nodule continue to enlarge or grow past 4 cm. As these nodules get bigger, they can cause symptoms and worsening overproduction of hormones. Eventually, large nodules can cause issues such as pain, flank and belly pressure/discomfort. As adrenal nodule size increases so too does the likelihood of the symptoms mentioned above becoming noticeable. If adrenal nodule size reaches 4 cm, or your nodule is large enough to cause symptoms, then adrenal surgery is usually recommended.
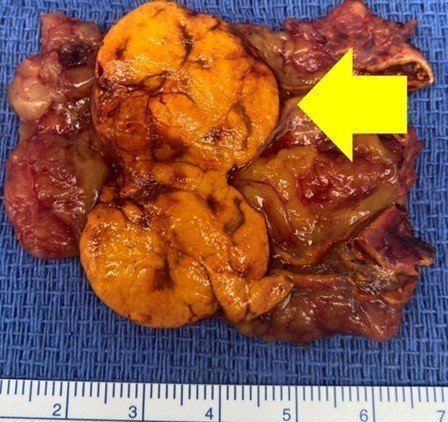
Figure 3. Typical 3 cm adrenal nodule (arrow) after it has been removed by surgery. This nodule produced too much cortisol causing Cushing’s syndrome.
#3 Thing to Know About Adrenal Nodule Size: Small Adrenal Nodules Can Be Dangerous
While most adrenal nodules are not cancerous as noted above, a small percentage are. Adrenal nodule size correlates with the risk of it being cancerous. The risk of cancer increases substantially above 4 cm. All adrenal cancers start small, so just because an adrenal nodule is small does not mean it is benign.
Also, many small adrenal nodules overproduce hormones, which can make you very sick. In fact, most aldosterone-producing adrenal tumors are between 0.5-2.0 cm. These nodules are very small but pack a powerful punch. The overproduction of aldosterone can lead to high blood pressure, stroke, and heart attacks. The problem is the toxic levels of aldosterone, a very potent and dangerous hormone. Read more about primary aldosteronism, or Conn's Syndrome.
Also, small adrenal tumors can be pheochromocytomas or cortisol-producing adenomas. Both of these types of tumors can cause severe illness. Cortisol-producing adenomas cause adrenal hypercortisolism (AHC), formerly called MACS or subclinical Cushing syndrome, and Cushing’s syndrome when it is severe.
Read more on this:
- Best adrenal operation for pheochromocytoma
- Top 5 myths about adrenal Cushing's syndrome
- Adrenal gland surgery: What you should know
#4 Thing to Know About Adrenal Nodule Size: Expert Adrenal Nodule Imaging is Important
The first imaging study used in work-up and evaluation of adrenal nodule size and any adrenal problem should always be an expert, skilled, dedicated adrenal-protocol CT scan. Adrenal CT scan is the best and most common method for evaluating adrenal nodules.
An adrenal CT scan can help determine adrenal nodule size and the density of the nodule. (On a CT scan without contrast, a density of 10 Hounsfield units or less indicates a lipid-rich, benign adenoma.) This test can also be used to check the number of nodules, and adrenal nodule size. Additionally, this method is excellent to look for adrenal cancer that has spread outside the adrenal gland.
In fact, a CT scan is often what incidentally identifies the adrenal nodule in the first place. This is technically called an “adrenal incidentaloma”. The definition of an adrenal incidentaloma (nodule) is an adrenal lesion that is discovered when a radiological study (often CT scan) is performed for indications other than for adrenal disease (e.g., belly pain, car accident, etc.). That means it was discovered incidentally, or by accident. These adrenal incidentalomas should never be ignored. They need to be evaluated properly with lab testing and further studies.
Read more on adrenal incidentaloma.
Adrenal Nodule Size: Summary
Adrenal nodules are very common. Adrenal nodule size is certainly important but is not the only clinical factor that determines whether surgery, surveillance, or other treatment is needed. Not all large nodules are bad, and not all small nodules are benign. Many both small and large nodules may overproduce hormones causing illness, which can be cured by surgery. Adrenal nodule surgery, involving partial or the whole adrenal, is often necessary to diagnose and cure these nodules, regardless of adrenal nodule size. Large nodules, symptomatic ones, nodules that are growing, and ones that are atypical or suspicious often require adrenal nodule surgery. The first imaging test used in work-up and evaluation of adrenal nodule size and any adrenal problem should always be an expert, skilled, dedicated adrenal CT scan.
Expert evaluation and treatment for adrenal nodules are paramount. Our team of adrenal experts is here to help and guide you every step along the way and will be there for you after your adrenal nodule surgery. To learn more and become a patient, please see our resources below.
Additional Resources:
- Learn more about the Carling Adrenal Center
- Learn more about Dr. Tobias Carling
- Learn more about our sister surgeons at the Norman Parathyroid Center, Clayman Thyroid Center and Scarless Thyroid Surgery Center
- Learn more about the Hospital for Endocrine Surgery