Atypical Adrenal Masses: Why Small Tumors Can Still Mean Big Cancer Risks—and What to Do About It

Atypical Adrenal Masses: Why Small Tumors Can Still Mean Big Cancer Risks—and What to Do About It
Imagine getting a routine scan for an unrelated issue, and your doctor identifies a small mass on your adrenal gland. At around 2 cm, it seems minor, and the usual advice might be to monitor it. However, a significant study in The Journal of Clinical Endocrinology & Metabolism (2025, Vol. 110, No. 7) changes that perspective. It reveals that atypical adrenal masses, even those smaller than 4 cm with unusual imaging characteristics like high density (elevated Hounsfield Units or HU on CT scans), carry a substantial risk of being cancerous.
This multicenter research, based on data from 2000 to 2020, emphasizes the importance of evaluation and, in many cases, removal. As the founder of the Carling Adrenal Center, one of the highest-volume adrenal surgery centers in the world, I've seen how prompt action with the right technique can improve outcomes. Let's review the findings, their implications, and why surgery—particularly our Mini Back Scope Adrenalectomy (MBSA)—is often the best approach.
.jpg)
What Are Atypical Adrenal Masses?
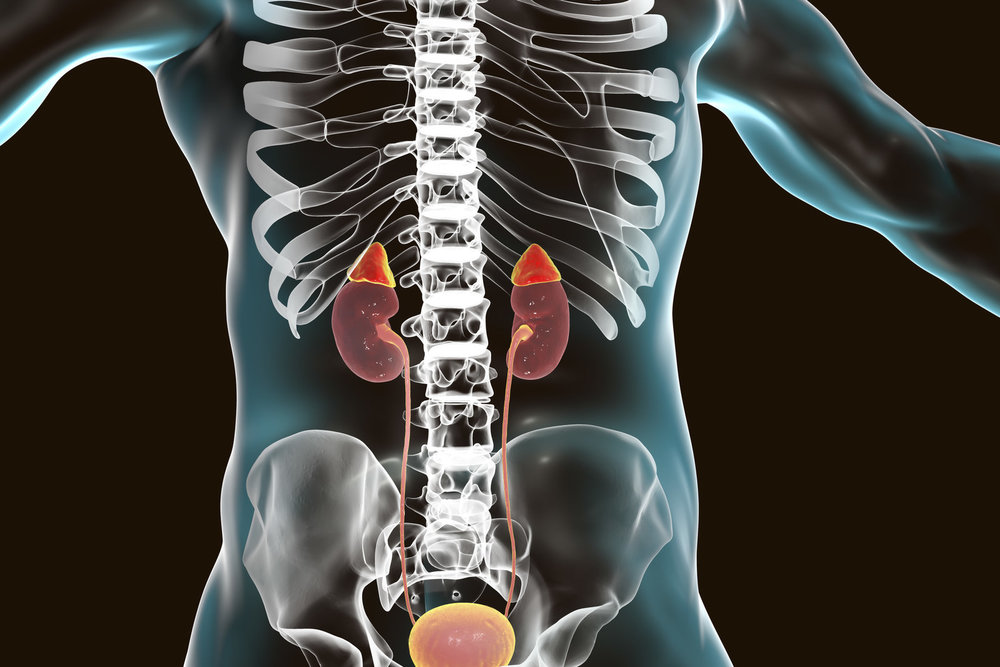
Adrenal masses are frequently discovered, affecting 5-7% of adults who undergo abdominal imaging. Most are benign adenomas, appearing as low-density lesions (<10 HU) on CT due to their lipid content. Atypical adrenal masses show higher density (>10 HU) and account for a substantial share of these discoveries. In general, they can include pheochromocytomas (tumors that disrupt blood pressure regulation), metastases, or adrenocortical carcinomas (ACCs)—aggressive cancers that can spread if not addressed.
The study examined 217 adults (224 masses) with tumors at least 1 cm, followed for a minimum of 6 months. It excluded pheochromocytomas, metastases, cases with prior treatments and clear non-tumors like hemorrhages. The cohort was 61.3% female, with a median age of 58; masses were typically incidental (77.7%), detected on CT (80.1%), and unilateral (98%). Pathological analysis of 71 masses—primarily from surgery —uncovered concerning patterns.
The Cancer Risk Hiding in Small Sizes
The central insight: Size alone doesn't determine safety. Traditional guidelines often suggest observation for masses under 4 cm, but these atypical ones had a median size of about 2 cm initially, and 25 were confirmed ACCs. The cancers grew much faster (a median of about 12.9 mm per year) than benign adenomas (about 0.3 mm per year), and growth of more than about 2.7 mm per year was the best cut-off for separating malignant from benign masses.
Why You Should Care
Atypical adrenal masses represent more than incidental findings—they can lead to significant health issues. ACC is uncommon but dangerous: 5-year survival is about 82% for stage I and 61% for stage II disease, but falls to about 50% for stage III and 13% for stage IV, which is why finding it early matters so much. The study addresses limitations in prior research, highlighting growth trends that call for revised management strategies. Risks extend to hypertensive crises from pheochromocytomas or indicators of other underlying conditions.
For patients, these discoveries can cause concern, affecting diverse groups—unilateral masses, slightly more common on the left. The key message? Unusual imaging warrants a thorough endocrine review to prevent hormonal imbalances or malignant progression.
Time to Act: Get It Removed
Observation may suit very low-risk cases, but for atypical adrenal masses with concerning features, surgery is generally recommended. Guidelines advocate removal for suspicious lesions, and in our view this study supports earlier intervention for high HU or growth (the authors themselves conclude that long-term imaging surveillance is warranted when surgery is deferred). Biopsies are not recommended; complete evaluation provides definitive diagnosis and resolution.
The method matters. In our experience, conventional robot-assisted or laparoscopic surgery through the abdomen involves a longer operation and recovery.
The Carling Adrenal Center: Our Approach to Safe Removal
At the Carling Adrenal Center in Tampa, Florida, we specialize exclusively in adrenal conditions and are one of the highest-volume adrenal surgery centers in the world. Our Mini Back Scope Adrenalectomy (MBSA) sets the standard—this approach uses a small posterior incision for direct access, bypassing the abdomen.
Why Choose MBSA:
- Minimally Invasive: Small incisions mean less pain and minimal scarring.
- Fast: The operation typically takes about 20 minutes.
- Quick Recovery: Patients usually go home the next morning and return to normal routines within days, not weeks.
- Reduced Risks: Low complication rates, avoiding abdominal organ involvement.
- Effective: Complete tumor removal, well-suited for these smaller atypical masses. Very large tumors and known adrenal cancers may need a different approach.
At the Carling Adrenal Center, you receive comprehensive care, from pre-op hormone assessments to ongoing monitoring. About half of our patients come from outside Florida, including from around the world.
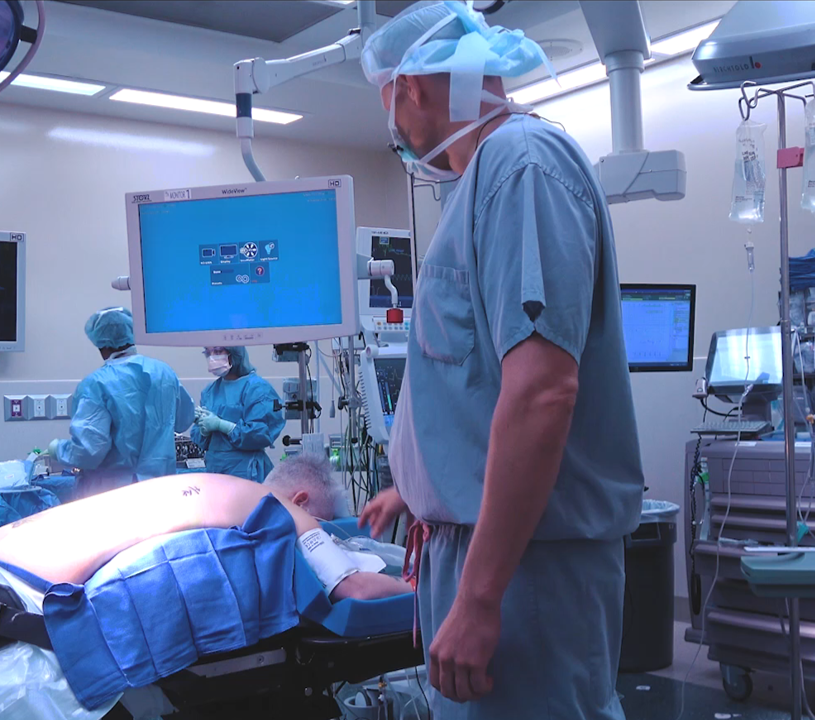
Figure 1: Dr. Carling inspecting that the positioning of the patient is perfect prior to proceeding with Mini Back Scope Adrenalectomy (MBSA).
Steps You Can Take Right Now
If an adrenal mass is identified:
- Seek Specialized Evaluation: Consult an adrenal expert for HU analysis and hormone testing.
- Monitor Changes: If surgery is not indicated right away, then follow up with imaging in 6-12 months; rapid growth calls for action.
- Prioritize Removal: For atypical masses under 4 cm with elevated HU, opt to get it removed—MBSA offers a straightforward, effective solution.
- Manage Related Conditions: Address blood pressure or metabolic concerns that could compound issues.
- Stay Informed: Review your imaging and collaborate with a specialist team.
Moving Forward
This research study shifts the focus, advocating guidelines that prioritize imaging characteristics over size alone. While retrospective with some constraints, it opens doors to future studies on underlying mechanisms, perhaps leading to alternative treatments.
If you have an atypical adrenal mass, take control: Get it removed safely and promptly to minimize cancer risks. Contact the Carling Adrenal Center—we're ready to help you navigate this and regain your health.
Reference
Balderrama-Brondani V, Al-Ward R, Kiseljak-Vassiliades K, et al. Clinical and Radiological Features of Atypical Adrenal Masses: A Multicenter Retrospective Study. J Clin Endocrinol Metab. 2025;110(7):e2183-e2190.
Additional Resources:
- Learn more about the Carling Adrenal Center
- Learn more about Dr. Tobias Carling
- Learn more about our sister surgeons at the Norman Parathyroid Center, and Clayman Thyroid Center.
- Learn more about the Hospital for Endocrine Surgery