What is an Adrenal Incidentaloma?
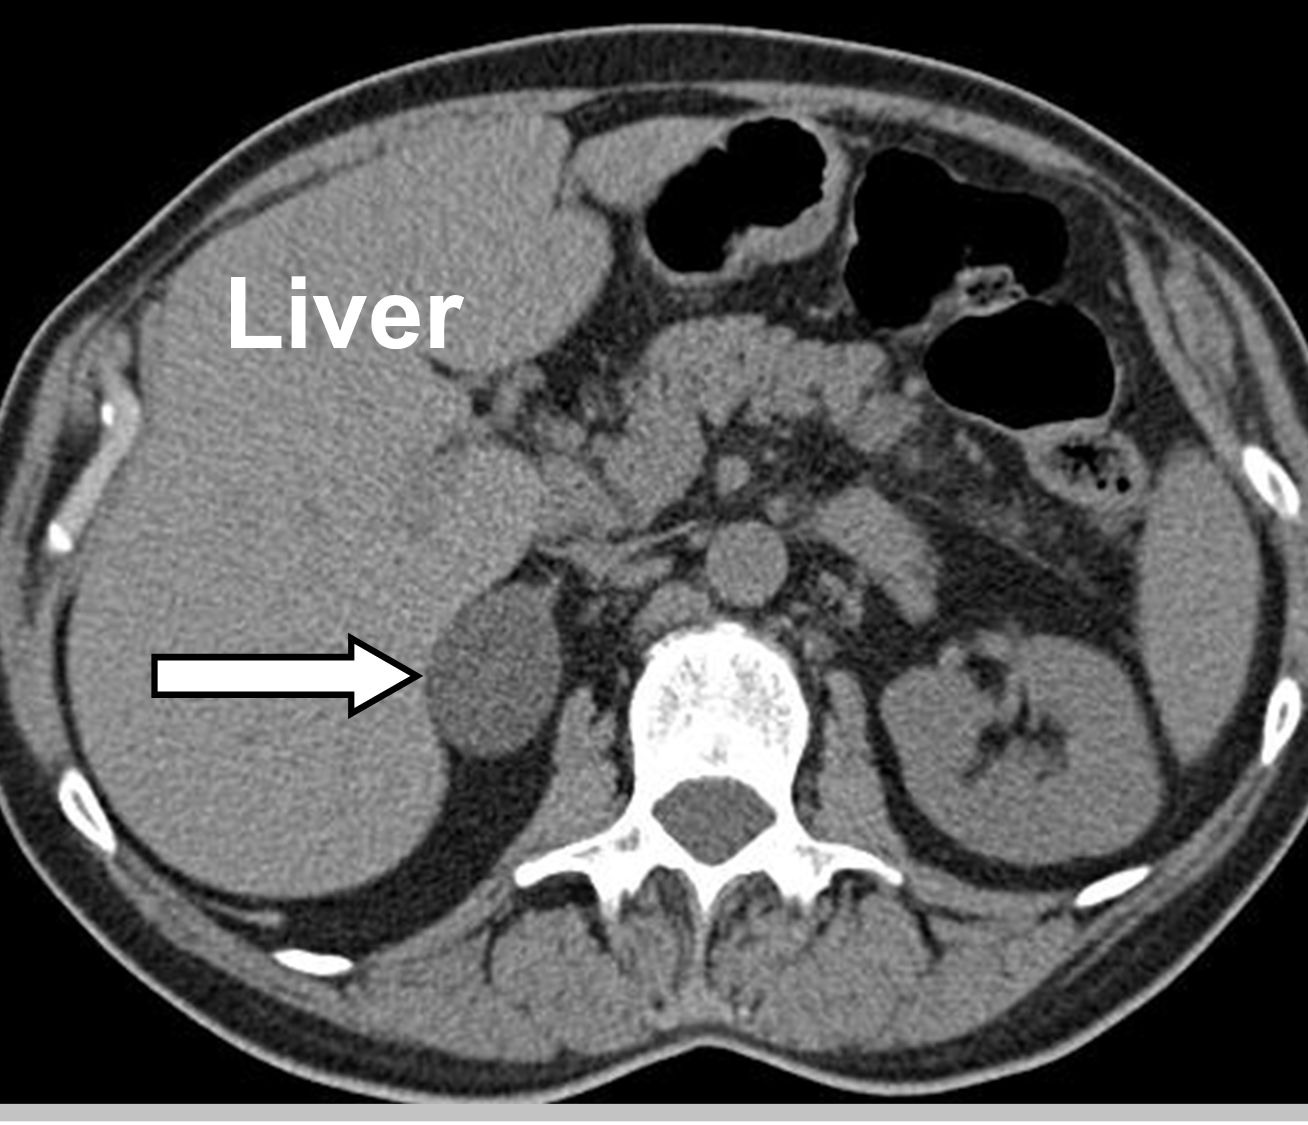 A non-contrast CT scan displaying a right adrenal incidentaloma (arrow). All incidentally identified adrenal tumors need to be worked up to ensure they do not overproduce hormones or are cancerous.
Are Adrenal Incidentalomas Common?
Adrenal incidentalomas are quite common, and become more common as we age. About 4–7% of adults have an adrenal tumor, and more with age, so you can imagine that lots of people having a CT scan will have an adrenal tumor found that they didn't know about. They are uncommon in young adults; an adrenal mass in a young person, a child or during pregnancy deserves prompt attention.Are Adrenal Incidentalomas Cancer?
The large majority of adrenal incidentalomas are benign and not cancer. Size alone does not decide: the appearance on the scan, hormone function and growth matter more, although tumors over 4 cm deserve particular attention. About half to two thirds make no excess hormone; the rest do, most often cortisol, and usually without obvious symptoms. This is why "benign on the scan" does not mean "nothing to do": every adrenal incidentaloma needs hormone testing. A tumor that grows quickly must be assumed to be malignant until proven otherwise; read more about the risk of cancer in adrenal tumors and about adrenal cancers.What the CT scan tells us: Hounsfield units. On a CT scan done without contrast, the density of the tumor is measured in Hounsfield units (HU). A uniform tumor measuring 10 HU or less is rich in fat (lipid-rich) and is a benign adenoma. A tumor above 10 HU, or one that looks irregular or uneven, is "indeterminate": many are still benign, but the scan alone cannot prove it. Read more about CT, MRI and PET scans for adrenal tumors.
Do I need repeated scans? Follow-up depends on the imaging appearance and the hormone results, not on a fixed schedule. Benign-appearing (10 HU or less), non-secreting masses generally need no repeated imaging. Indeterminate masses need further evaluation (additional imaging now, or a repeat scan after 6 to 12 months) or removal. Hormone-producing tumors should be evaluated for surgery whatever they look like on the scan.
It should be noted, however, that most studies of risk of adrenal tumors found incidentally are flawed in one way or another. Yes, medicine is not a perfect science. For instance, some research studies that have looked at this may be affected by small sample size; inclusion of a patient population who were referred to tertiary centers (introducing bias into the study), inclusion of patients with a history of cancer or suspicion of malignancy (this will increase the rate of identifying adrenal metastasis), and exclusion of patients with small tumors.
Other Cancers Commonly Spread to the Adrenal Glands
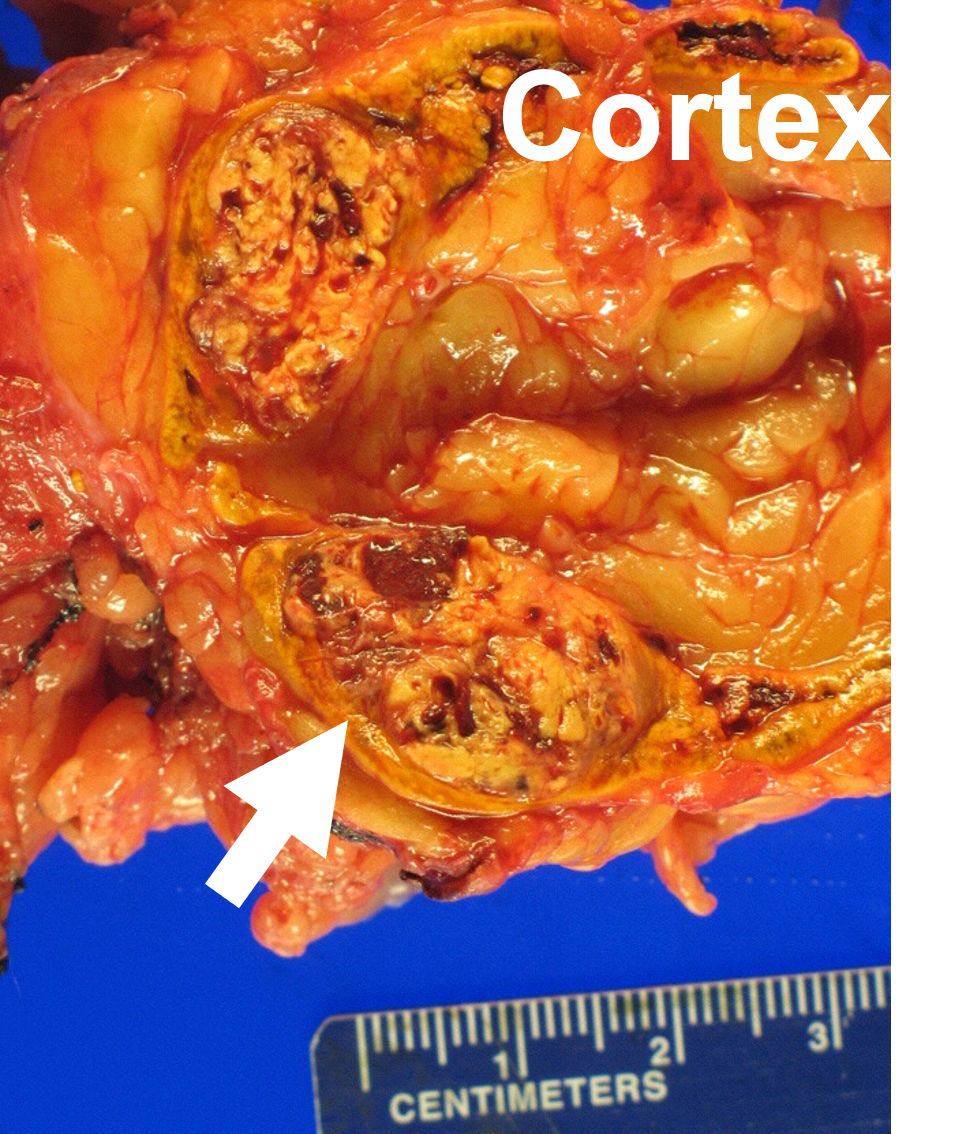 Adrenal metastasis from a stage 4 kidney cancer (renal cell carcinoma) within the adrenal gland.
- Lung cancer (Primarily non-small cell lung cancer; NSCLC)
- Kidney cancer (Renal cell carcinoma)
- Malignant melanoma
- Breast cancer
- Colon & Rectal cancer
- Stomach cancer (Gastric carcinoma)
- Esophageal cancer
- Liver cancer (Hepatocellular carcinoma)
- Lymphoma
What Tests Do You Do for Adrenal Incidentalomas?
When clinicians face an adrenal incidentaloma, there are mainly three questions that need to be answered:- Is the mass truly arising from the adrenal? This is usually easy to tell based on the CT or MRI scan. However, there are some rare retroperitoneal lesions that may be adjacent but not arising from the adrenal gland, per se.
- Is the adrenal incidentaloma a cancer (malignant), and if so, is it a primary adrenal cancer (the cancer started in the adrenal gland) or is it a metastatic cancer that came from another organ?
- Is the incidentaloma functional (overproducing hormones)? Every patient with an adrenal incidentaloma should have the specific hormone tests listed below, together with a history and physical exam aimed at finding a functional tumor or an underlying malignant disease.
The tests every adrenal incidentaloma needs:
- 1-mg overnight dexamethasone suppression test (DST), together with ACTH and DHEA-S, to look for cortisol excess. You take one 1-mg dexamethasone tablet at 11 pm and have your blood cortisol measured the next morning. A cortisol above 1.8 µg/dL is abnormal and indicates adrenal hypercortisolism (AHC), formerly called MACS (mild autonomous cortisol secretion) or subclinical Cushing syndrome. A result of 1.2–1.8 µg/dL is "possible AHC": it must be interpreted together with ACTH and DHEA-S (both are typically low in AHC) and is worth repeating.
- Aldosterone and renin (the aldosterone-to-renin ratio, ARR) if you have high blood pressure or a low potassium, to look for primary aldosteronism (PA).
- Plasma free metanephrines or 24-hour urine fractionated metanephrines, to look for a pheochromocytoma.
- Non-contrast CT density in Hounsfield units, as described above.
- Sex hormones and steroid precursors (such as DHEA-S, testosterone and estradiol) when adrenal cancer is suspected.
A 24-hour urine cortisol and a late-night salivary cortisol are usually normal in mild and moderate AHC, so normal results on those tests do not rule it out. Read more about laboratory tests for adrenal tumors.
AHC is the most common hormone excess found in adrenal incidentalomas, and it is linked to high blood pressure, diabetes, bone fractures and heart disease even when a patient does not look like they have Cushing syndrome. Adrenalectomy is the only cure. In mild AHC the decision is individualized, based on cortisol-related health problems, whether one or both glands are involved, age, surgical risk and your preference. In a randomized trial (CHIRACIC, Lancet Diabetes & Endocrinology 2025), adrenalectomy improved blood pressure control compared with conservative care (46% versus 15% met the blood pressure goal).
Important: It is crucial that you seek out an adrenal specialist who can help you answer these questions to ensure you receive the appropriate treatment.Bottom Line: What an Adrenal Incidentaloma Usually Turns Out to Be
-- Nonfunctional adenoma about half to two thirds
-- Adrenal hypercortisolism (AHC; formerly MACS or subclinical Cushing syndrome) the most common hormone excess
-- Primary aldosteronism (Conn's syndrome) about 2-5%
-- Adrenocortical carcinoma rare
2) Adrenal medullary tumors
-- Pheochromocytoma about 1-5%
3) Metastasis from another distant cancer uncommon unless you have a known cancer
4) Other causes (such as myelolipoma, cysts or bleeding) uncommon
Last updated October 2026.