What Blood Tests and Hormone Tests are Needed for Adrenal Tumors?
After performing a very careful interview of the patient to see if they have any signs and symptoms of adrenal hormone excess, the next step is to perform laboratory testing to see if the adrenal tumor is overproducing any hormones. Knowing what hormone is being produced (if any), and how much, is critically important. Unfortunately, testing for hormone production from adrenal tumors tends to confuse both patients and physicians, but it shouldn't. The reason is that many doctors see only a few adrenal patients a year and have limited experience with obtaining and interpreting adrenal hormone tests. The tests themselves are simple, and most can be ordered by your primary care doctor.
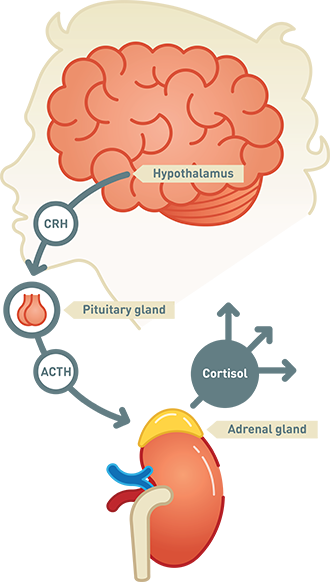 Cortisol production is controlled by another hormone called ACTH, produced by the pituitary. When testing for adrenal hypercortisolism (AHC), it is important to measure both cortisol and ACTH levels.
Blood Tests and Urinary Tests. The correct laboratory evaluation is mostly done with blood tests, sometimes with a 24-hour urine collection. There are laboratory tests that are first done to screen for the three main hormone problems: adrenal hypercortisolism (AHC), formerly called MACS (mild autonomous cortisol secretion) or subclinical Cushing syndrome; primary aldosteronism (PA), also called Conn's syndrome or primary hyperaldosteronism; and pheochromocytoma. We discuss all of these tests in depth within the sections dedicated to each adrenal tumor type. Sometimes these laboratory tests are unequivocal (i.e. the diagnosis is a slam dunk), and the patient can go straight to curative surgery (Mini Back Scope Adrenalectomy (MBSA) is our preferred operation for the great majority of patients).
Sometimes, however, these laboratory tests are borderline or difficult to interpret because of interference by medications. You can always contact us to review laboratory tests. This is all we do. For us it is very easy to evaluate laboratory testing since we have seen thousands of adrenal patients. Sometimes when the laboratory tests are borderline they have to be repeated. In addition, there are some confirmatory tests that may need to be performed. For a detailed discussion of the laboratory evaluation (blood, urine and other tests) of each condition, go to the individual pages on pheochromocytoma, adrenal hypercortisolism (Cushing syndrome), primary aldosteronism (Conn's syndrome), and adrenocortical cancer. If your tumor was found by accident on a scan, see adrenal incidentaloma.
Testing for sex-hormone excess is also advocated by the European Society of Endocrinology, which recommends testing for DHEA-S, androstenedione, 17-hydroxyprogesterone, testosterone for women and estradiol for men and post-menopausal women if there are clinical signs of virilization or suspicion of adrenal cancer.
Remember, most hormone-producing adrenal tumors, and tumors over 4 cm that are not clearly benign on CT, should be removed surgically. Size alone does not decide: the appearance on the scan, hormone function and growth matter more. For most patients, the Mini Back Scope Adrenalectomy (MBSA) is, in our experience, the best operation. Choose your surgeon carefully, because experience matters. Contact the Carling Adrenal Center if you have any questions.
What Are the Most Common and Important Tests for Adrenal Tumors?
Every adrenal tumor needs a 1-mg overnight dexamethasone suppression test (DST) with ACTH and DHEA-S, plasma or urine metanephrines, and, if you have high blood pressure or a low potassium, aldosterone and renin. The most commonly used and important blood, urine and other tests are listed here:
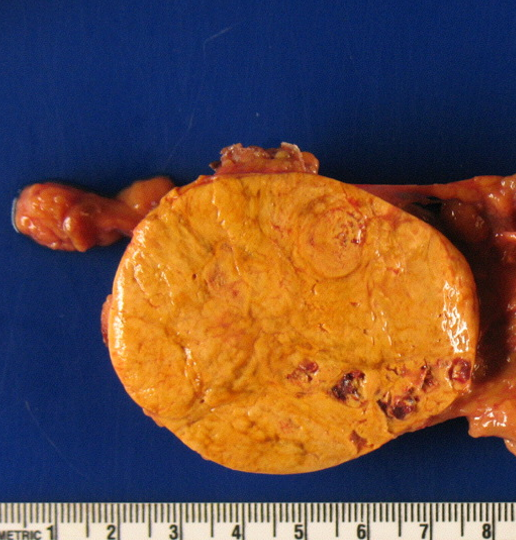 Typical adrenal adenoma overproducing cortisol, causing adrenal hypercortisolism (adrenal Cushing syndrome).
- Testing for Pheochromocytoma (medulla-arising tumors)
- Blood Test
- Plasma free metanephrines (metanephrine and normetanephrine): a recommended first test
- 24h Urine Collection
- Urine fractionated metanephrines (metanephrine and normetanephrine): the alternative first test
- Plasma or urine catecholamines and VMA are no longer recommended as the first tests
- Testing for Adrenal Hypercortisolism, Primary Aldosteronism and Adrenal Cancer (cortex-arising tumors)
- Tests for adrenal hypercortisolism (AHC, high cortisol)
- 1-mg overnight dexamethasone suppression test (DST): the key test for every adrenal tumor. A morning cortisol above 1.8 µg/dL is abnormal (mild 1.8–5.0, moderate 5–10, severe above 10 µg/dL). A result of 1.2–1.8 µg/dL is "possible AHC": it must be interpreted together with ACTH and DHEA-S and is worth repeating
- ACTH (low: below 20 pg/mL in mild, below 10 in moderate and below 5 in severe AHC)
- DHEA-S (typically low)
- Late-night salivary cortisol testing (saliva test): usually normal in mild and moderate AHC, so a normal result does not rule it out
- 24h urine collection for UFC = Urinary Free Cortisol: usually normal in mild and moderate AHC, so a normal result does not rule it out
- Tests for primary aldosteronism (PA, high aldosterone)
- Plasma aldosterone concentration
- Renin (plasma renin activity or direct renin concentration; low)
- Aldosterone-to-renin ratio (ARR)
- Potassium (K+; low in only a minority of patients, so a normal potassium does not rule out PA)
- 24h urine collection for aldosterone (a confirmatory test used in selected patients)
- 1-mg DST: every patient with PA should have one, because 13–27% also make excess cortisol
- Adrenal vein sampling (AVS) is not a laboratory test but an interventional radiology procedure used in selected patients to show which gland is overproducing aldosterone; it is not needed for every patient
- Tests for Sex-Steroid Hormones and Adrenal Cancer
- Testing for AHC and PA as above
- DHEA-S
- 17-OH-Progesterone
- Androstenedione
- Total Testosterone
- Free Testosterone
- 17-Beta-estradiol (serum, only in men and postmenopausal women)
Note: When you have the disease, these tests are typically high (elevated), except those indicated as low, which are classically reduced. Several common medications can interfere with these tests, so tell your doctor everything you take. For PA screening, beta-blockers and clonidine can cause false-positive results, while spironolactone, eplerenone, diuretics, ACE inhibitors and ARBs can cause false negatives.
Last updated October 2026.