What is Primary Aldosteronism (Conn's Syndrome)?
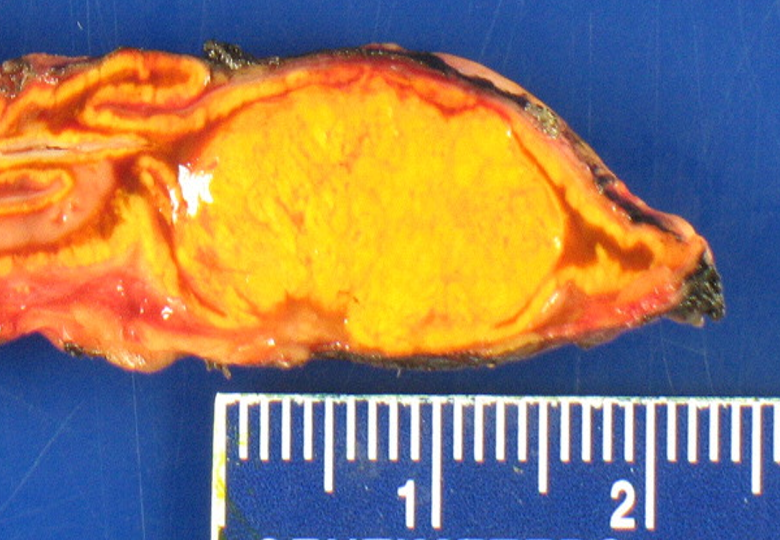 A typical aldosterone-producing adenoma (APA), causing primary aldosteronism (Conn's syndrome).
Primary aldosteronism (PA) is a disease in which one or both adrenal glands make too much of the hormone aldosterone on their own, without the body asking for it. The extra aldosterone can come from a single benign tumor, from several small nodules, or, rarely, from overgrowth of the whole gland. PA was first described by Dr. Jerome Conn, which is why it is also called Conn's syndrome (or Conn syndrome); many doctors call it primary hyperaldosteronism. PA is the most common cause of secondary hypertension (secondary hypertension means that the high blood pressure has a known cause and is potentially curable). When a single benign tumor is responsible, it is called an aldosterone-producing adenoma (APA). Yes, in these patients the whole problem is caused by a small (but toxic) benign tumor of the adrenal gland, and surgery is the only treatment that can cure it.
Is Primary Aldosteronism Rare?
No. Primary aldosteronism is not rare; it is common. PA affects an estimated 5-20% of all people with high blood pressure, and we see patients with it every week. PA was long thought to be rare because it was rarely tested for: many patients did not feel very sick, so the disease was not diagnosed and the patients were simply treated with blood pressure pills (anti-hypertensives).Unfortunately, over time, too much aldosterone damages your heart, blood vessels, kidneys and brain (read about the complications of primary aldosteronism). The 2025 Endocrine Society guideline now recommends that everyone with high blood pressure be screened for PA with a blood test for aldosterone and renin. Even so, it is estimated that fewer than 1% of people with PA are ever diagnosed.
Low Potassium and High Aldosterone: Is Low Potassium Required?
Low blood potassium is the classic finding in patients with aldosterone-producing tumors of the adrenal gland. For decades it was thought that you could not have PA unless the blood potassium was low, and many doctors were taught in medical school that primary aldosteronism cannot exist with a normal potassium level. Therefore, the question is: Do you need low blood potassium to have primary aldosteronism? No. Most patients with PA have a normal potassium level; only a minority are hypokalemic (have low blood potassium). A normal potassium should never be a reason not to test for PA. Unless you are tested, you will not know. Because fewer than 1% of people with PA are ever diagnosed, many go untreated and may suffer strokes, heart attacks and heart failure unnecessarily.Can Primary Aldosteronism (Conn's Syndrome) be Cured?
Often, yes. When the excess aldosterone comes from one adrenal gland, surgery cures the hormone problem in the large majority of patients (about 94% in a large international study). Blood pressure becomes completely normal without any medication in roughly a third to a half of patients, and improves in most of the rest, who usually need fewer pills. Patients who are younger, female, have had high blood pressure for a shorter time, take fewer medications and have no kidney damage have the best chance of coming off blood pressure medication entirely. This silent disease can often be cured by a short mini-scope operation, typically taking about 20 minutes. Growing evidence shows that adrenalectomy for PA lowers the risk of future strokes, heart attacks, arrhythmias (for instance atrial fibrillation) and premature death, and most patients feel better. Learn how the Mini Back Scope Adrenalectomy (MBSA) is done. When both glands are involved or the disease is mild, medications called mineralocorticoid receptor antagonists (spironolactone, eplerenone) work well for many patients. Read more about the symptoms of PA, about what is called “target organ damage” and about reduced quality of life in PA on other pages of this site.
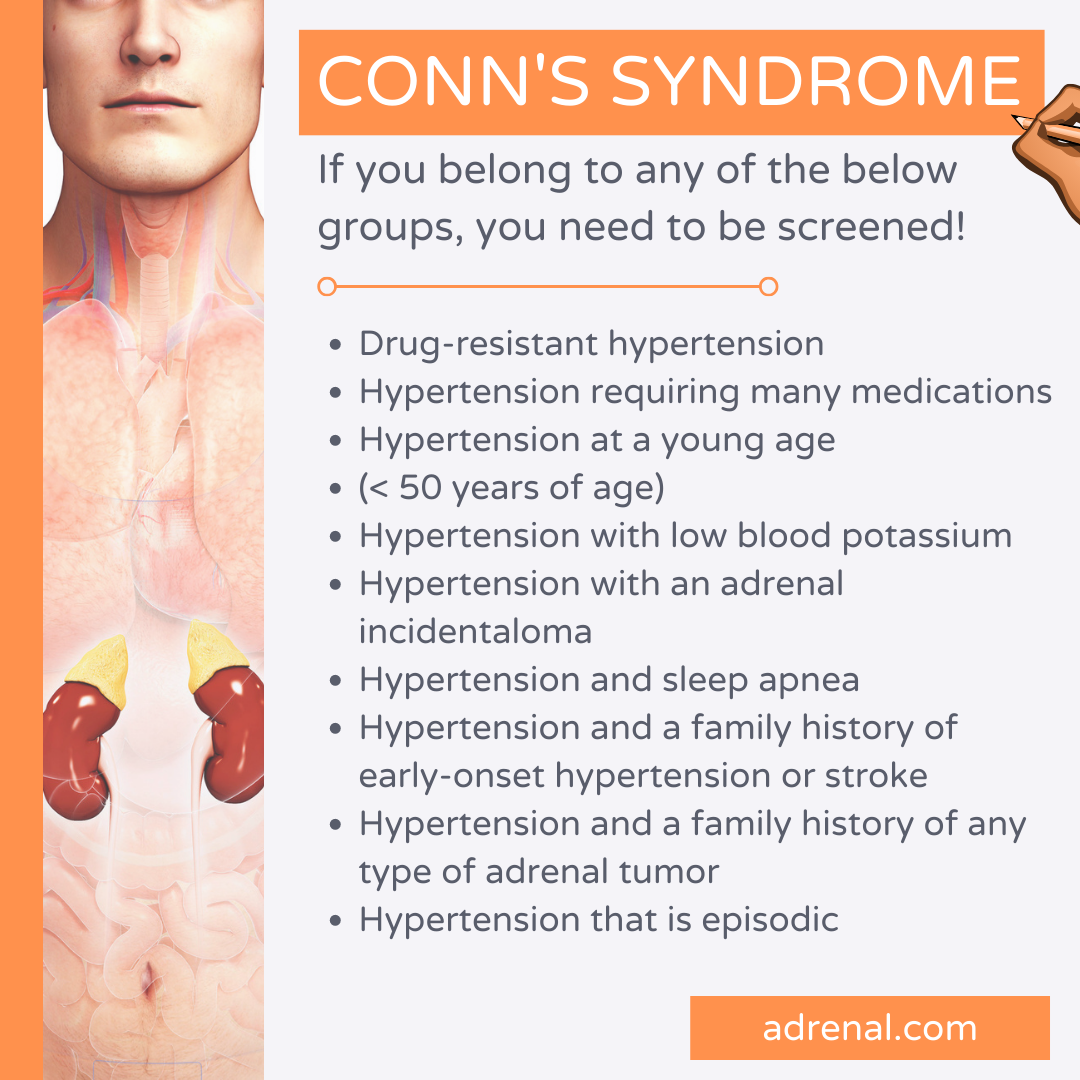 Who should be screened for primary aldosteronism (Conn's syndrome)? Everyone with high blood pressure should be tested once; the groups shown here are at especially high risk. Screening is easy. Ask your doctor for a simple blood test of your aldosterone and renin levels.
Types of Primary Aldosteronism: What the Pathology Shows (HISTALDO)
After surgery, every PA specimen should be stained for aldosterone synthase (CYP11B2), the enzyme that makes aldosterone. This staining, classified by an international system called HISTALDO, shows exactly which cells were making the hormone:- Aldosterone-producing adenoma (APA): a single tumor of 1 cm or larger (classic)
- Aldosterone-producing nodule (APN): a single nodule smaller than 1 cm (classic)
- Multiple aldosterone-producing nodules or micronodules (MAPN/M) (non-classic)
- Aldosterone-producing diffuse hyperplasia (APDH) (non-classic)
- Rare causes: inherited (familial) forms of PA and, very rarely, aldosterone-producing adrenocortical carcinoma
How is Primary Aldosteronism Diagnosed?
The diagnosis of primary aldosteronism (Conn's syndrome) follows a logical three-step approach:- Screening for the disease. This is done with blood tests for aldosterone, renin and potassium. The result is expressed as the aldosterone-to-renin ratio (ARR). Potassium may be low but is normal in most patients.
- Confirming the disease. The blood tests are repeated; additional confirmatory testing is needed only in selected patients. Because 13-27% of patients with PA also make too much cortisol, every patient with PA should also have a 1-mg dexamethasone suppression test.
- Finding the source. A CT scan of the adrenal glands is performed and, in selected patients, adrenal vein sampling (AVS), to learn whether one or both glands are responsible.
Not every patient needs adrenal vein sampling. Read who does and who does not on our adrenal vein sampling (AVS) page, and more on our adrenal surgery blog
Last updated October 2026.