What are the Symptoms of High Aldosterone (Primary Aldosteronism)?
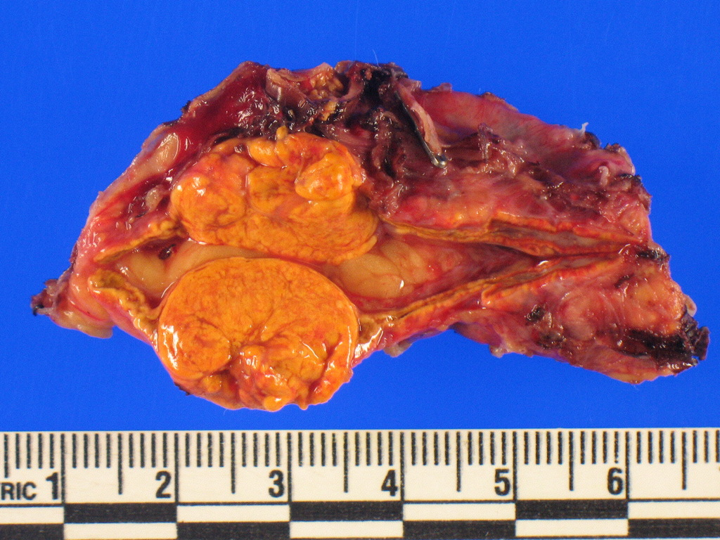 A typical adrenal tumor producing excess aldosterone, causing primary aldosteronism (Conn's syndrome).
If your adrenal gland is overproducing aldosterone, you have a disease called primary aldosteronism (PA), also called Conn's syndrome after Dr. Conn, who first described this disease. High blood pressure is the main sign of excess aldosterone. Other signs and symptoms of PA include low potassium in the blood (in a minority of patients), frequent urination, especially at night, muscle cramps and heart palpitations (feeling your heart racing). PA can also cause what doctors call "neurocognitive" symptoms. These symptoms describe how we feel, and how our brain works. Many patients report fatigue, poor and unrefreshing sleep, headaches, anxiety, depression, and memory difficulties or "brain fog". If you have high blood pressure and low potassium, you should definitely be tested to make sure you do not have PA, but remember that most patients with PA have a normal potassium level.
Almost all patients with PA have high blood pressure. Everyone with high blood pressure should be tested once for PA. This matters even more if you are relatively young and have no other risk factors such as diabetes or a family history of high blood pressure. It is important to know that many patients with PA have no symptoms at all. They may feel normal, and the only sign is high blood pressure. However, if PA is left untreated, patients have a much higher risk of stroke, heart attack and heart arrhythmias than people with ordinary high blood pressure of the same severity: about 2.5 to 4 times the risk of stroke, 2.6 to 6.5 times the risk of heart attack, and 3.2 to 12 times the risk of atrial fibrillation. Read more about the complications of primary aldosteronism.
Do All Patients with Primary Aldosteronism Have Symptoms?
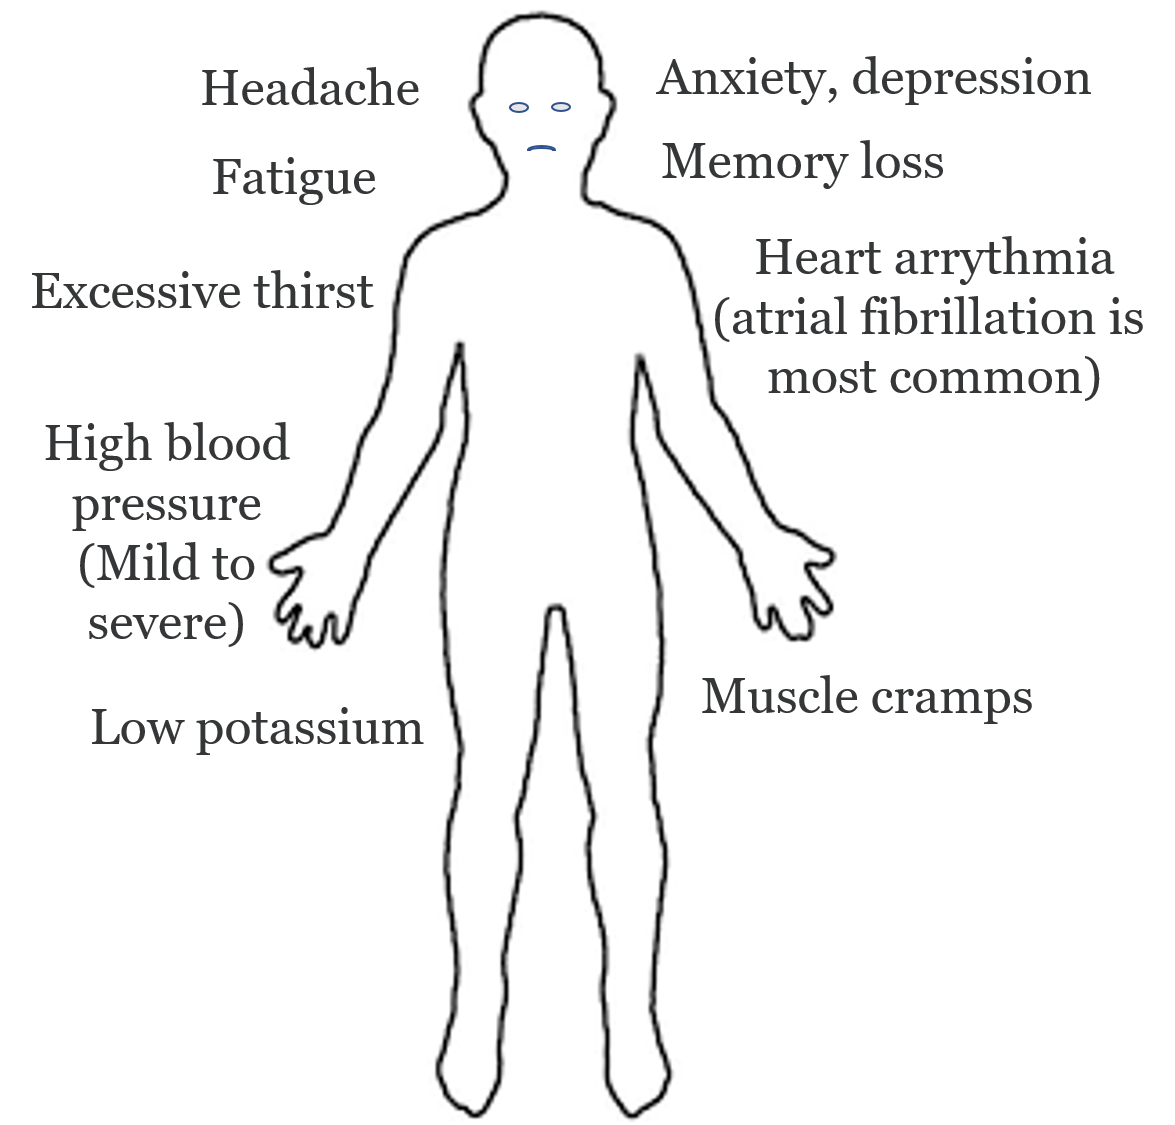 Signs and symptoms of primary aldosteronism (Conn’s syndrome): Many patients feel normal (asymptomatic) apart from high blood pressure. The symptoms, if present, can be variable.
No. Often, the only sign that anything is wrong may be hypertension (mild to severe high blood pressure). Low blood potassium (hypokalemia) is present in only a minority of patients; when it is, the patient may have nocturia (urination at night), polyuria (frequent urination), muscle cramps, weakness and palpitations (a racing heartbeat). Aldosterone levels in PA tend to be at their worst at night and in the early morning, which is a plausible reason why so many patients sleep poorly and wake up feeling unwell. Remember, many patients are completely asymptomatic. This means they have no symptoms at all. This is why it is so important to screen patients with high blood pressure; otherwise they go undiagnosed and untreated, leading to unnecessary complications such as heart arrhythmias, stroke, heart attacks and premature death.
The Need for Screening for Primary Aldosteronism. An estimated 5-20% of all people with high blood pressure have underlying PA that has not been diagnosed. Nearly half of American adults have high blood pressure, which means that millions of Americans have PA. Fewer than 1% of them are ever diagnosed, and an even smaller fraction are offered surgery. For patients whose excess aldosterone comes from one adrenal gland, a minimally invasive adrenalectomy, typically taking about 20 minutes, cures the hormone problem in the large majority. Surgical removal of the adrenal tumor may save you from developing future strokes, heart attacks, arrhythmias (for instance, atrial fibrillation) and premature death. This is why everyone with high blood pressure needs to be screened for this disease.
Who Should be Tested for High Aldosterone (Primary Aldosteronism)?
Everyone with high blood pressure should be screened once for PA; this is what the 2025 Endocrine Society guideline recommends. Screening is easy. Ask your doctor to check, with a simple blood test, your plasma aldosterone concentration (PAC) and your renin (plasma renin activity, PRA). Dividing the aldosterone by the renin gives the aldosterone-to-renin ratio (ARR). If your renin is low and the ARR is greater than 20, you may have PA. This screening test is the ARR test. Read more about testing for primary aldosteronism. Testing is especially urgent if you belong to any of the groups below. If you do, print this page, bring it to your doctor and ask to be screened for primary aldosteronism (Conn's syndrome).- Drug-resistant hypertension (i.e. blood pressure that is not controlled well with medications)
- Hypertension requiring many medications
- Hypertension requiring being on Spironolactone (Aldactone), Eplerenone (Inspra) or Amiloride
- Hypertension of any grade, especially without known risk factors such as advanced age, kidney problems, diabetes, obesity, etc.
- Hypertension at a young age (< 50 years of age)
- Hypertension with low blood potassium (hypokalemia)
- Hypertension with an adrenal incidentaloma (any adrenal tumor on CT scan)
- Hypertension and sleep apnea
- Hypertension and a family history of early-onset (< 50 years of age) hypertension or cerebrovascular accident (stroke) at a young age
- Hypertension and a close family member with primary aldosteronism
- Hypertension and atrial fibrillation
Last updated October 2026.