What Do the Adrenal Glands Do?
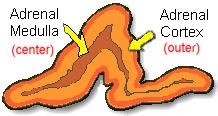
Adrenal glands produce hormones required for healthy life. The adrenal cortex produces hormones that control salt balance and blood pressure (aldosterone), blood sugar, metabolism and the response to stress (cortisol), and weak sex hormones (adrenal androgens such as DHEA). The adrenal medulla produces hormones involved in the fight-or-flight response (catecholamines: adrenaline, also called epinephrine, and noradrenaline, also called norepinephrine).The Adrenal Medulla and Cortex Produce Very Different Hormones. We have two adrenal glands located on the top of both kidneys. They are orange-colored, triangular-shaped and about the size and shape of a fortune cookie. Each gland consists of a medulla (the center of the gland) which is surrounded by the cortex.
Function of the Adrenal Medulla: Adrenaline
The adrenal medulla is responsible for producing catecholamines, or adrenaline-type hormones. We have all experienced that sudden panic feeling and anxiety when something happens suddenly and unexpectedly and we get scared. All of a sudden we have tingles and we feel like we need to run away or stand up and fight. This is the "fight-or-flight" response and it is caused by the sudden release of adrenaline from our adrenal glands. (Yes, adrenaline is called this because it comes from the adrenal gland.) The adrenal medulla produces two main hormones: adrenaline (called epinephrine in the United States) and noradrenaline (norepinephrine). A tumor of the medulla that makes too much of these hormones is called a pheochromocytoma.
Function of the Adrenal Cortex: Cortisol and Aldosterone
The adrenal cortex produces aldosterone, which is necessary for fluid and electrolyte (salt) balance and blood pressure, and cortisol, which controls metabolism, blood sugar and the body's response to stress. Too much aldosterone causes primary aldosteronism (PA, also called Conn's syndrome). Too much cortisol (high cortisol) from the adrenal gland is called adrenal hypercortisolism (AHC), formerly called MACS (mild autonomous cortisol secretion) or subclinical Cushing syndrome. The adrenal cortex also makes small amounts of weak sex hormones but this only becomes important if overproduction is present (most sex hormones are produced by the testes and ovaries). The three layers of the adrenal cortex are: Microscopic view of the adrenal cortex: The layers of the adrenal gland cortex, zona glomerulosa (ZG), fasciculata (ZF), and reticularis (ZR), which produce aldosterone, cortisol, and adrenal androgens.
- The zona glomerulosa (ZG) is the most superficial layer of the adrenal cortex and it produces the mineralocorticoid (salt-regulating) hormone aldosterone.
- The zona fasciculata (ZF) is the middle zone of the adrenal cortex, and it primarily produces cortisol.
- The zona reticularis (ZR) is the innermost zone of the adrenal cortex and it is adjacent to the adrenal medulla. The zona reticularis makes adrenal androgens (weak sex hormones such as DHEA, DHEA-S and androstenedione), which the body can convert to testosterone and estrogen in small amounts.
Technical Information for Doctors and Nurses.
In the zona glomerulosa (ZG), progesterone is converted through several steps to the mineralocorticoid aldosterone. In the other layers of the cortex, progesterone is converted first to 17-hydroxyprogesterone and then to either the 17-hydroxysteroid cortisol or the 17-ketosteroid adrenal androgens. The final steps of aldosterone production require the enzyme aldosterone synthase (CYP11B2), which is why every adrenal specimen removed for primary aldosteronism should be stained for CYP11B2. Each day the adrenal glands secrete milligram amounts of cortisol and androgens but only microgram amounts of aldosterone.
The mineralocorticoid aldosterone is produced in the outermost layer of the adrenal cortex, the zona glomerulosa. Aldosterone secretion is primarily controlled through a renal pathway (the renin-angiotensin system) and by the serum potassium level. Decreased arterial pressure and decreased delivery of sodium chloride to the kidney tubule are sensed by the juxtaglomerular apparatus and the macula densa, respectively. The result is the production and release of renin, which generates angiotensin I. Within the lung, angiotensin-converting enzyme (ACE) converts most of the angiotensin I to angiotensin II. Circulating angiotensin II stimulates aldosterone secretion, as does elevated serum potassium. To a lesser degree, aldosterone secretion is stimulated by ACTH. With aging, there is decreased production of aldosterone. In primary aldosteronism, aldosterone is produced independently of this pathway, so renin is suppressed; this is the basis of screening with the aldosterone-to-renin ratio (ARR).
The zona fasciculata (ZF) is responsible for glucocorticoid production, and the zona reticularis (ZR) mainly produces adrenal androgens. Secretion of cortisol is controlled via the hypothalamic-pituitary-adrenal (HPA) axis. Hypothalamic corticotropin-releasing hormone (CRH) causes release of adrenocorticotrophic hormone (ACTH) from the anterior pituitary gland, which stimulates the adrenal cortex to release cortisol. As the cortisol concentration rises, it exerts a negative feedback on both the hypothalamus and anterior pituitary secretion. Cortisol follows a daily rhythm, peaking in the early morning and falling to its lowest level around midnight. ACTH has a plasma half-life of minutes and cortisol has a plasma half-life of about 60 to 90 minutes. ACTH and cortisol production is constant over life in normal, unstressed individuals. A cortisol-producing adrenal tumor ignores this feedback: ACTH is suppressed, DHEA-S is typically low, and cortisol remains above 1.8 µg/dL the morning after a 1-mg overnight dexamethasone suppression test. This is the basis of testing for adrenal hypercortisolism (AHC). Adrenal androgen release is regulated by ACTH, whereas gonadal release of testosterone and estrogen are under a separate pathway of pituitary-gonadotrophic control. Androgen production peaks at puberty and progressively declines with advancing age.
Stimulation of the adrenal medulla is via preganglionic sympathetic fibers causing release of dopamine, norepinephrine and epinephrine. Sympathetic neural outflow is increased by the fight-or-flight response, fear, emotional stress, upright posture, pain, cold, hypotension, hypoglycemia and other stress. Norepinephrine exerts negative feedback at the preganglionic sympathetic receptors. With increasing age, there is no change in epinephrine levels, but norepinephrine and total plasma catecholamine are increased.
Read more about the Mini Back Scope Adrenalectomy (MBSA). This is our preferred adrenal operation, used for more than 95% of our operations. Most people with an adrenal tumor do not need surgery, but every adrenal tumor needs hormone testing.
Last updated October 2026.