Why Do You Need to Take Primary Aldosteronism Seriously?

Because too much aldosterone is toxic. High aldosterone levels damage the heart, blood vessels, kidneys and brain; this is called Target Organ Damage. We are passionate about educating patients and doctors because today fewer than 1% of all patients with PA are diagnosed, and an even smaller fraction are offered curative surgery. This silent disease can often be cured by a Mini-Back Scope Adrenalectomy (MBSA), an operation that typically takes 20 to 30 minutes. PA is important not only because it is very common (an estimated 5-20% of people with high blood pressure have it), but also because patients with PA have a much higher rate of cardiovascular disease and death. It is silent and dangerous. Compared with people of the same age and sex who have essential hypertension (high blood pressure NOT related to the adrenal glands) of the same severity, patients with PA have about 2.5 to 4 times the risk of stroke, 2.6 to 6.5 times the risk of heart attack and 3.2 to 12 times the risk of atrial fibrillation (an irregular heart rhythm).

Why is primary aldosteronism so important, and why are we so eager to get patients treated? Treating one-sided PA by surgery ( Mini-Back Scope Adrenalectomy; MBSA) cures hypokalemia, lowers blood pressure, reduces the number of antihypertensive medications required, and improves measures of heart and kidney function. Read more about surgery for primary aldosteronism. Even if surgery is not for you (maybe your PA is mild or comes from both adrenal glands, or you are at a very advanced age with multiple other illnesses), we want you to be diagnosed accurately, because there are medications that specifically block the effects of aldosterone. These are the mineralocorticoid receptor antagonists (spironolactone and eplerenone). They work well for mild or two-sided PA and for patients who are not candidates for surgery, and newer drugs (aldosterone synthase inhibitors) are emerging. For one-sided disease we believe surgery is the better choice, because it is the only treatment that removes the source.

How Does High Aldosterone Damage the Heart, Blood Vessels, Kidneys and Brain?
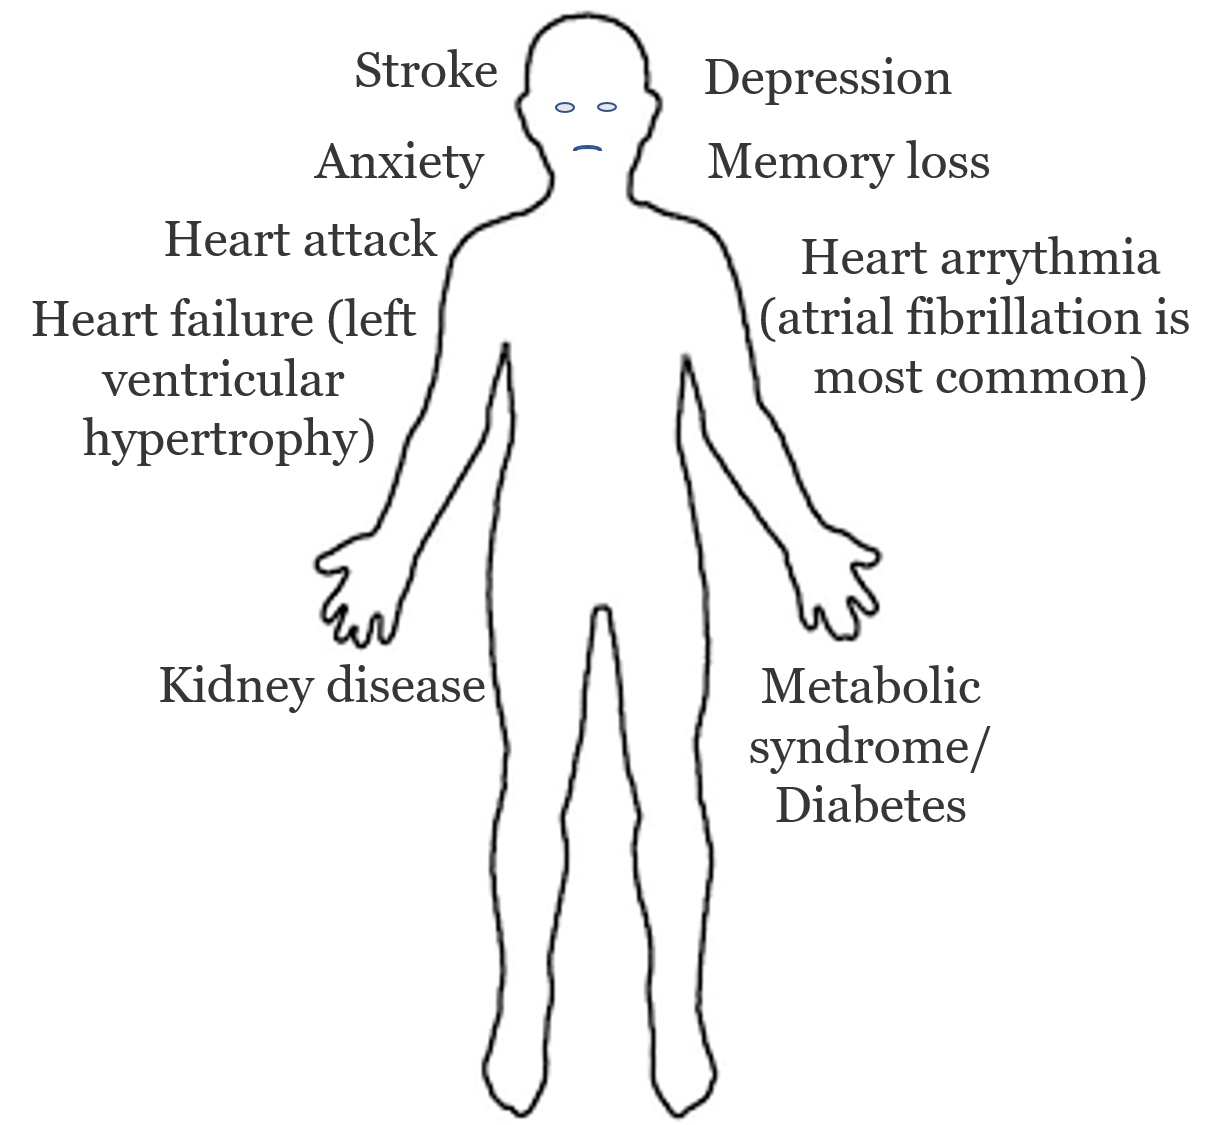
Complications of primary hyperaldosteronism (Conn’s syndrome): The consequences of undiagnosed and untreated Conn’s syndrome. Complications of primary aldosteronism (Conn’s syndrome): The consequences of undiagnosed and untreated disease. Remember, too much aldosterone (often from an aldosterone-producing adrenal adenoma) harms your body. This harm is called Target Organ Damage. Traditionally, aldosterone was considered simply the main regulator of salt and water balance, through its effects on the kidney and colon. Its actions in other tissues were much less evident, but studies in both humans and animal models over the past few decades have shown that its effects are mainly targeted at the heart, blood vessels, kidney, and central nervous system (CNS). Please note that the discussion below is somewhat technical.
Damage to your heart

The main harmful effects of aldosterone excess on the heart are inflammation in and around the blood vessels, fibrosis (scarring), and thickening of the heart muscle (myocardial hypertrophy). Animal studies have shown that excess aldosterone promotes heart muscle thickening, remodeling and scarring independent of blood pressure (this is bad for your heart). Studies in patients show that PA is associated with more frequent and more severe left ventricular hypertrophy (this is when the heart muscle grows too thick and does not function properly). This is an effect of aldosterone itself, not just of the blood pressure: patients with PA have more severe abnormal heart growth than patients with essential hypertension (high blood pressure without aldosterone excess), even after correction for age, sex, and the duration and severity of hypertension. PA also greatly raises the risk of atrial fibrillation, which in turn raises the risk of stroke.

Damage to your blood vessels

Too much aldosterone is toxic to the inner lining of blood vessels called the endothelium, leading to increased risk of stroke, heart attack, arrhythmia, kidney failure, and premature death. Too much aldosterone is toxic to the inner lining of blood vessels called the endothelium, leading to increased risk of stroke, heart attack, arrhythmia, kidney failure, and premature death. The inflammation that too much aldosterone causes in the heart muscle can also be observed in blood vessels elsewhere, through similar mechanisms (this is harmful inflammation in your vessels: the arteries and veins responsible for transporting blood throughout your body). Aldosterone causes problems with relaxation of your vessels through its effect on their inner lining (this is called endothelial dysfunction). Aldosterone also increases vascular stiffness. In patients with PA, research has shown more fibrosis (scar formation) in the walls of the small resistance arteries.

Damage to your kidneys

Too much aldosterone is very bad for your kidneys. In fact, many of our patients with PA already have damage to their kidneys (increased creatinine and reduced glomerular filtration rate; GFR) even before they are referred to us. Many studies in animal models of aldosterone excess have shown that aldosterone contributes to kidney disease. The good news is that adrenalectomy (read about Mini-Back Scope Adrenalectomy ) helps protect the kidneys in the long term. One thing to know: kidney function (eGFR) may appear to drop in the first months after PA is cured. This is not new damage. Excess aldosterone makes the kidneys over-filter, which masks damage that is already there; once the hormone is back to normal, the true kidney function shows, and it then usually stabilizes. No one wants to end up dependent on a dialysis machine, so if you have high blood pressure and slowly worsening kidney function, you need to make sure you do not have PA quietly harming your kidneys.

Damage to your brain (CNS; Central Nervous System)

The brain (CNS) is considered one of the main targets of aldosterone. Raised aldosterone levels in the CNS can increase blood pressure. The main consequence of aldosterone excess on the CNS is the predisposition to acute cerebrovascular events (stroke, etc), related to vascular damage that aldosterone may induce in the CNS vascular bed. To lower the risk of future devastating injuries to the brain, patients with PA should be treated correctly, often by surgery. Learn more about Mini-Back Scope Adrenalectomy (MBSA).

Damage to your Quality of Life (QoL)

Quality of life (QoL) studies aim to measure how we feel and how our brains work, and how a disease affects our daily lives. PA has been shown in many studies to reduce quality of life. The good news is that this is reversible. This means you can feel better after curative adrenalectomy. In most studies, adrenalectomy not only substantially improves the QoL of patients with PA but restores it to the level of the general population. This means that you are likely to get back to your baseline after curative surgery. The reduced QoL tends to be related to anxiety, depressive symptoms, psychological distress, fatigue, lack of energy, poor sleep, reduced activity level, various emotional problems, body pain and aches, etc. (see the symptoms of primary aldosteronism). The reduced quality of life tends to be especially pronounced in younger, often female, patients.

Last updated October 2026.

Become Our Patient

Patients needing adrenal surgery travel from all over the world to have adrenal surgery with Dr. Carling, one of the world's most experienced adrenal surgeons. This page discusses how you can have your adrenal operation at the Carling Adrenal Center with Dr. Carling himself.

Become Our Patient Here