Who is the Best Adrenal Surgeon for Me?
The best adrenal surgeon for you is going to be a surgeon with a great deal of skill and experience in adrenal surgery. Adrenal operations are difficult, and they are complicated by the hormones that adrenal tumors produce. Since surgery is the only cure for a hormone-producing or cancerous adrenal tumor, you should find a surgeon with experience in all types of adrenal surgery so your specific needs are met. It is well worth your time to find a high-volume adrenal surgeon. Low-volume surgeons (performing fewer than 6 adrenal operations per year) have significantly higher complication rates than high-volume adrenal surgeons.
Our view: In published studies, 6 adrenal operations per year is often used as the cut-off for a "high-volume" adrenal surgeon. We think that is a low bar. Dr. Carling’s experience, having trained dozens of endocrine surgeons as the Chief of Endocrine Surgery at Yale University, is that a surgeon should perform at least 50 adrenal operations per year to be a true high-volume surgeon. Very few surgeons anywhere in the world do.
What are some of the things you should know about adrenal gland surgery? Read more on our adrenal surgery blog
The Importance of Surgeon Volume and Experience in Adrenal Surgery
If you have an adrenal tumor that needs surgery, one of the most important factors for a good outcome is your choice of adrenal surgeon. Typically, the best adrenal surgeon is one with a lot of experience, and that may not be the surgeon with the most experience in your city. For many people, this means traveling to another city to be operated on by a high-volume adrenal surgeon.The typical surgeon who performs adrenal surgery in the United States does about one adrenal operation per year. You read that correctly. More than 80% of adrenalectomies in the United States are performed by low-volume surgeons, and outcomes are better with surgeons who do the operation regularly. You, or your loved one, depend on having an experienced surgeon for the best outcome. When a surgeon says he or she is an expert at adrenal surgery on the strength of 6 adrenal operations (adrenalectomies) per year, that is a low bar. Would you call someone an experienced airline pilot who flies an aircraft only 6 times a year? Dr. Carling may perform more adrenal operations in a single day than the typical surgeon does in several years. It may seem that this paragraph is self-serving, but as a referral center for patients from around the world, we regularly see complications from operations done by surgeons who perform adrenal surgery only occasionally, and it breaks our hearts.
Don't endocrine surgeons perform adrenal surgery? Yes, and endocrine surgeons tend to have the most adrenal experience. But even among endocrine surgeons, many perform only a handful of adrenal operations per year. It is our opinion that few people would choose a surgeon for this operation if they knew that surgeon performed 5 of them per year. Ask your surgeon the obvious question: "How many adrenal operations did you perform in each of the last 3 years?" If they can't look you in the eye and give you a satisfactory answer, then please seek a second opinion. For many of you, this means you will need to travel, but let's face it: few people know anybody who has had an adrenal operation.
We realize we cannot operate on every patient in the world needing an adrenal operation, but you should identify the highest-volume adrenal surgeon available to you. Ideally, the best surgeon for adrenal tumors is an endocrine surgeon with a special emphasis on adrenal tumors.
Why Are There so Few High-Volume Adrenal Surgeons?
There are so few surgeons who do a lot of adrenal surgery because 1) there aren't many adrenal operations to be done, and 2) there are at least 4 different types of surgeons who perform an occasional adrenal operation. In a big city, there may be 25 surgeons who each perform 1 or 2 adrenal operations per year instead of 1 surgeon who performs 100 per year. This is unfortunate, and it is the reason the Carling Adrenal Center has patients referred by doctors from all over the world. The following doctors perform adrenal surgery, most of them only occasionally:- Endocrine surgeons
- Minimally invasive surgeons, whose main practice is hernia, intestinal, bariatric, gallbladder, gastric and reflux operations
- Surgical oncologists, whose main practice is cancer of the breast, skin, intestine, liver, pancreas and other organs
- Urologists, whose main practice is the kidney, bladder and prostate
What is the best way to choose your adrenal surgeon? Read more on our adrenal surgery blog
Which Adrenal Operation is Best for Me? How Does the Surgeon Decide?
An experienced adrenal surgeon will consider a number of factors when determining which adrenal operation is best for each patient as an individual. Although we believe most patients are best served by the Mini Back Scope Adrenalectomy (MBSA), which we use for more than 95% of our operations, the surgeon must look at several things to make sure the operation chosen is the best in that circumstance:
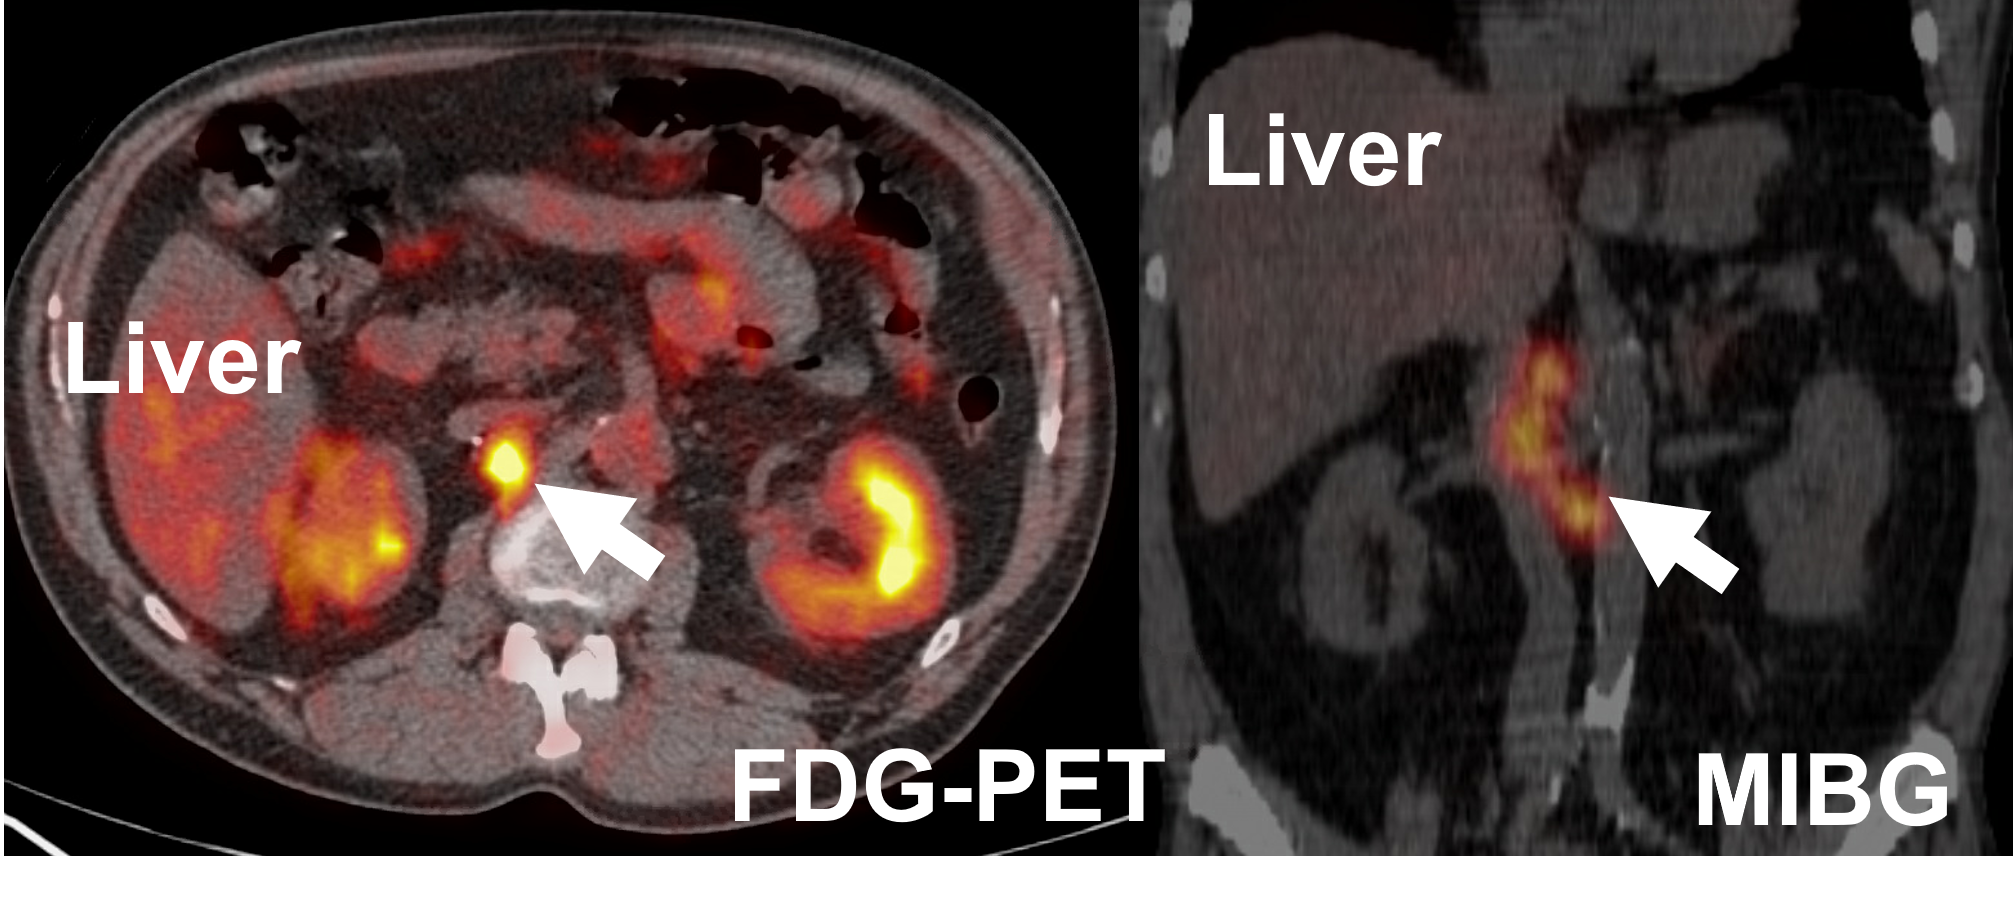 FDG-PET and MIBG scans demonstrating recurrent pheochromocytoma in the right adrenal bed (arrow) due to tumor spillage at the first operation. Dr. Carling removed the recurrence at a re-operation. The first operation was performed elsewhere.
- The size of the tumor. Since very large adrenal masses and tumors are more likely to be cancer, they may require a larger incision and a more careful dissection. When operating on adrenocortical cancer or pheochromocytoma, it is critical not to breach the capsule of the tumor and cause tumor spillage, a risk that is higher in inexperienced hands. Spilled tumor cells can implant into the surrounding tissue and make the tumor grow back (local recurrence). Additionally, it may be difficult to remove a very large adrenal tumor using scopes because the surgeon cannot see around the tumor with the camera. The MBSA suits most tumors, but very large tumors or known adrenal cancers may need a different approach, such as a laparoscopic hand-port assisted or an open adrenalectomy. This is discussed on our Eight Types of Adrenal Surgery page.
- The type of adrenal tumor. Adrenal cancers (adrenocortical cancer, and some metastatic pheochromocytomas or paragangliomas) usually require a larger, open operation to ensure all of the cancer is removed. This is especially true if the tumor is invading surrounding structures such as the kidney, liver, spleen, pancreas, bowel or major vessels such as the inferior vena cava (IVC). Open surgery remains the standard for known or suspected adrenal cancer. Often we do not know for sure whether an adrenal tumor is cancerous until the pathologist has examined it after the operation, so an experienced adrenal surgeon uses his or her best judgment, based on the scans and hormone tests, to decide which operation is the most appropriate.
- The appearance of the tumor on a CT, MRI, PET or other imaging study. It is crucial that the surgeon is expert in interpreting adrenal tumors on the various imaging studies. Cancers tend to look different on these scans from benign tumors. We have an entire page on imaging of adrenal tumors.
- A history of previous abdominal operations. If a patient has had previous abdominal operations, such as bariatric (weight loss), gallbladder, liver, stomach, bowel or gynecological surgery, scar tissue (adhesions) inside the abdomen can make a laparoscopic transabdominal adrenalectomy (the scope operation through the front of the abdomen) more technically difficult. An experienced laparoscopic surgeon can usually work through such scar tissue, so previous abdominal surgery does not rule out a minimally invasive operation. But one of the beautiful things about the MBSA is that the surgeon does not enter the abdominal cavity at all and does not need to deal with adhesions from a previous operation. We have a large page dedicated to this technique.
- The patient's body build. The MBSA is performed with the patient lying face down (prone), which does not suit every patient. The distance from the skin to the adrenal gland matters more than body mass index (BMI): the longer that distance, the more difficult the back approach.
- The surgeon's experience with different operations. Adrenalectomy is an uncommon operation, and many surgeons perform it only occasionally. As a referral center, we regularly see patients with complications after an operation by a surgeon who does adrenal surgery only a few times a year. It is hard to learn and maintain an advanced operation like the Mini Back Scope Adrenalectomy (MBSA) when you only do a few a year.
What About the Biopsy of My Adrenal Tumor?
A needle biopsy of an adrenal tumor is rarely helpful, and it should never be done before a pheochromocytoma has been ruled out with blood or urine tests (metanephrines), because it can be very dangerous to biopsy a pheochromocytoma. If the patient has an adrenocortical carcinoma (adrenal cancer), the biopsy may spill tumor cells, which can then implant and cause local recurrence. A needle biopsy also cannot reliably distinguish between a benign and a malignant adrenocortical tumor. The one accepted use of an adrenal biopsy is when a spread (metastasis) from a cancer elsewhere in the body is suspected and the result would change treatment. For everyone else, hormone tests and a good CT scan tell us more, and more safely. Read more about the work-up of an adrenal mass.

The most commonly performed adrenal operation is the laparoscopic transabdominal adrenalectomy (LTA; the front scope operation), and some surgeons use the robotic adrenal operation. Both can be done well by an experienced surgeon, and many high-volume adrenal surgeons use them. Published comparisons favor the back approach (MBSA) for operating time, pain and length of hospital stay, with similar complication rates, which is why we prefer it. A laparoscopic adrenalectomy through the abdomen typically takes 2 to 4 hours and a robotic adrenalectomy 3 to 5 hours, compared with about 20 minutes for an MBSA. Whatever operation you are offered, ask how many adrenal operations your surgeon performs each year. We have a large page dedicated to the MBSA.
Bottom line about finding the best adrenal operation. The best surgery is less about the technology being used and more about finding a knowledgeable, thoughtful surgeon who has a thorough understanding of adrenal anatomy, adrenal disease and adrenal tumors, and a great deal of experience in adrenal surgery. Reading the pages of this website, you have come to understand that the adrenal gland and its functions are complex, and indeed many patients and doctors struggle to obtain a comprehensive understanding of adrenal function and adrenal tumor disease. For us at the Carling Adrenal Center, this is what we do, day in and day out. Dr. Carling personally performs every operation. The number one priority is a safe operation without complications that cures the patient. Secondarily, we aim to do it quickly (minimizing anesthesia time), efficiently, and with an excellent cosmetic result.
Last updated October 2026.
What to read next
- Mini Back Scope Adrenalectomy (MBSA) - our preferred adrenal operation, used for more than 95% of our operations.
- More about our founder Dr. Tobias Carling - one of the world's most experienced adrenal surgeons.
- How to become our patient and have Dr. Carling perform your adrenal operation.