What is Adrenal Metastasis?
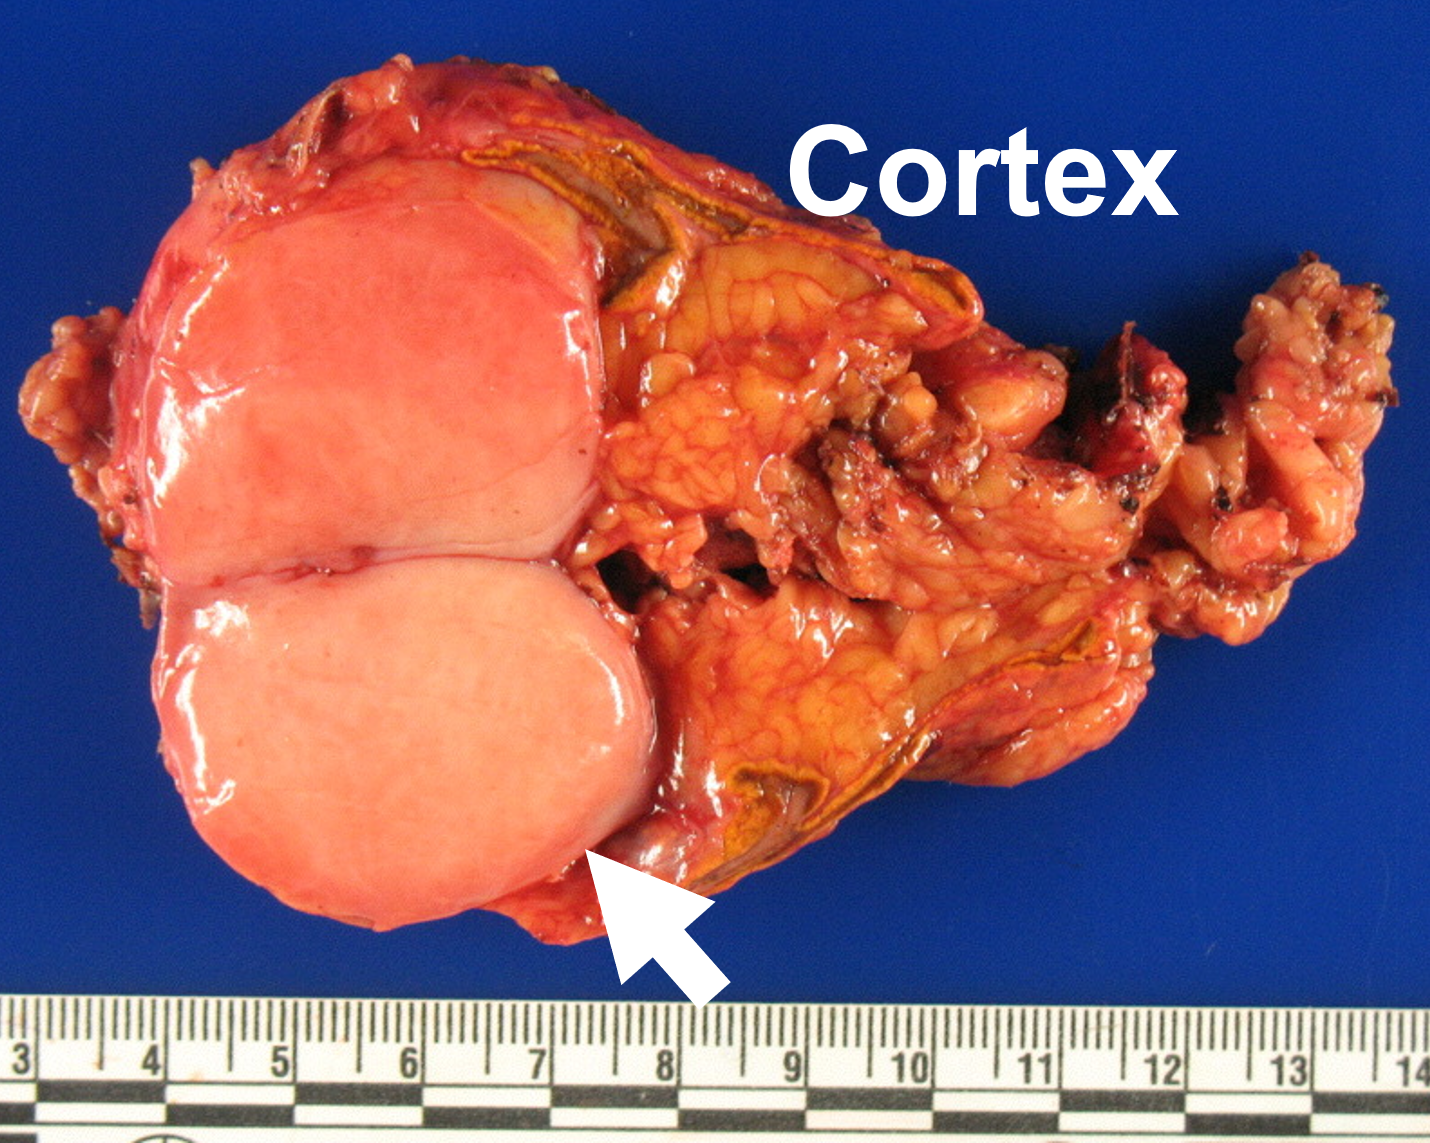 Adrenal metastasis from stage 4 lung cancer (non-small cell lung cancer; NSCLC; arrow) within the adrenal gland.
An adrenal metastasis is a cancer which has spread from another primary site to one or both adrenal glands. This is relatively common in many cancers. Nearly any cancer can spread to the adrenal glands, but some tumors are more likely than others to metastasize to this region. Having a cancer that has spread to the adrenal gland(s) means that the cancer is advanced (stage 4). However, if there is no other evidence of spread, complete surgical removal of an isolated adrenal metastasis offers the best-established chance of long-term control. The diagnosis of adrenal metastasis would rightly cause anyone concern, but an isolated adrenal metastasis can have a better outlook than spread to many other sites. Although prospective data (large high-quality scientific studies) are generally lacking, multiple retrospective (backward-looking) investigations have shown that adrenalectomy in selected patients with isolated or oligometastatic (meaning one or few areas of spread) disease from primary sites including the lung, melanoma, and kidney can result in longer survival compared with similar patients who do not undergo adrenalectomy. Because the patients in these studies were carefully selected, the results cannot be assumed for everyone.
The Carling Adrenal Center created this website to educate both patients and health care providers, including other doctors, about adrenal metastasis. We strongly believe that educated patients are much better equipped to face the challenges of overcoming their cancer.
What Cancers can Spread to the Adrenal Gland?
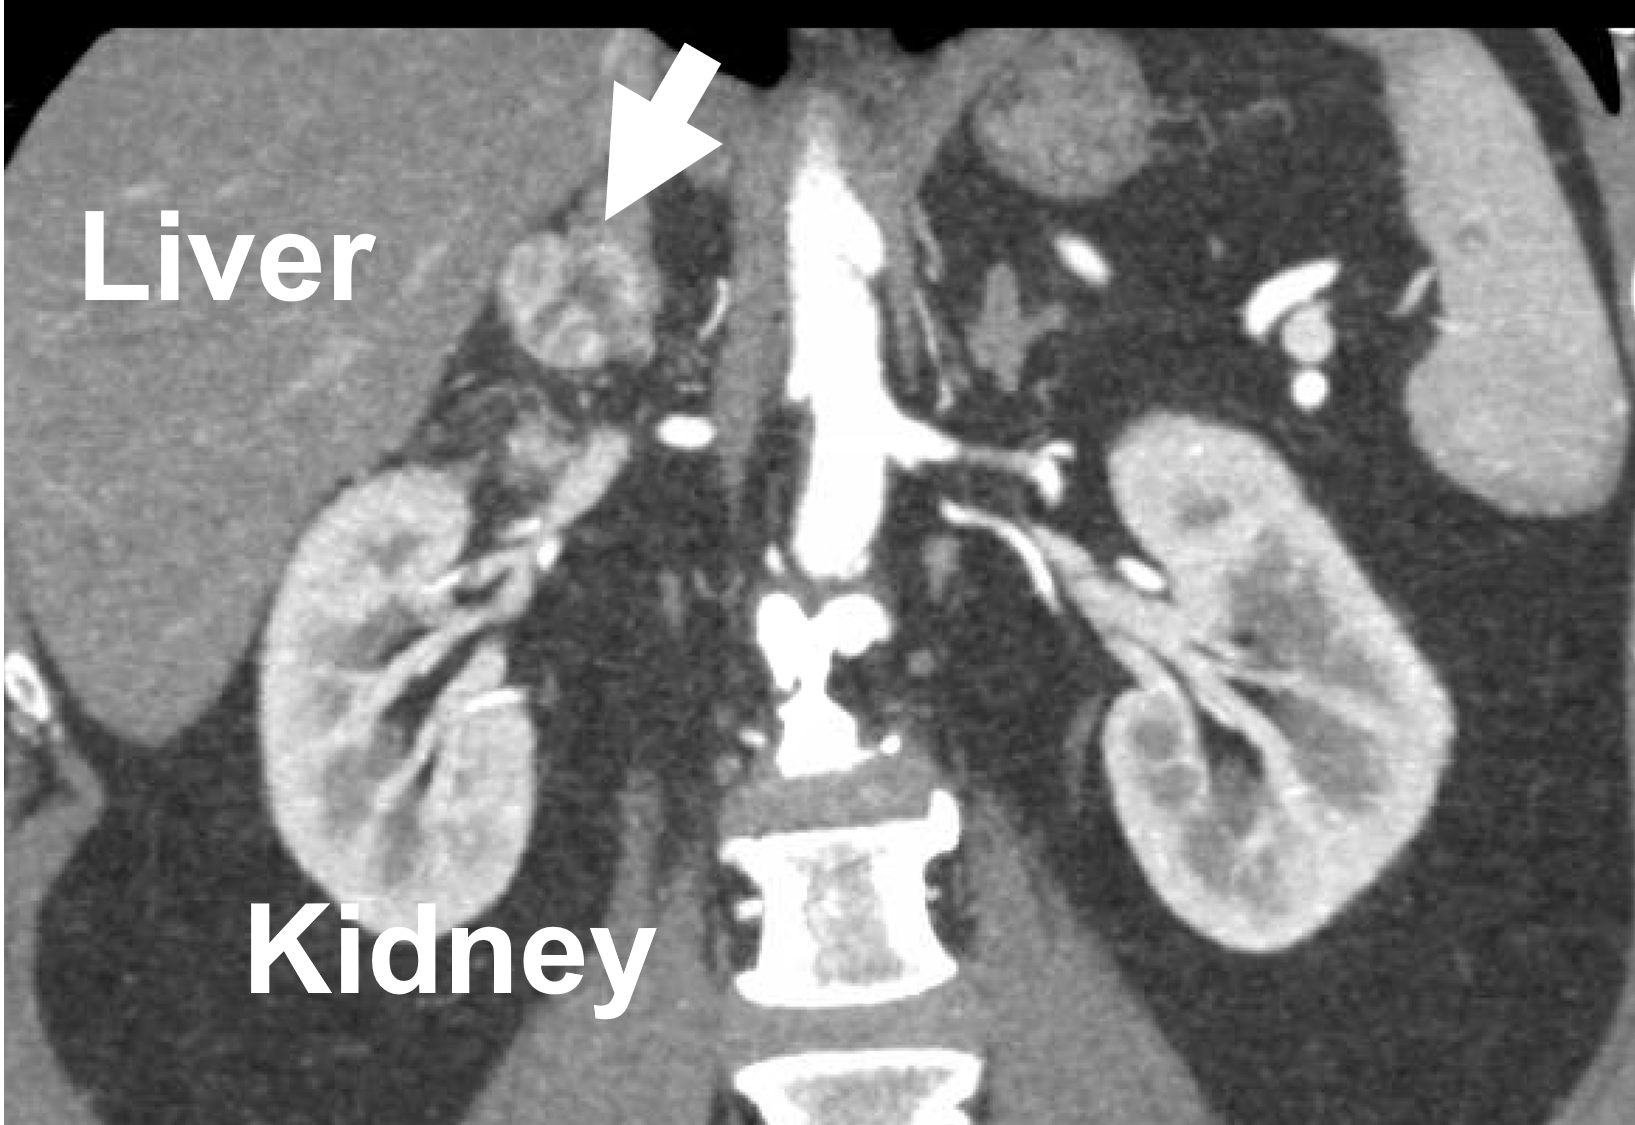 CT scan demonstrating a metastasis from renal cell (kidney) cancer to the right adrenal gland (arrow). Dr. Carling removed this tumor via the Mini Back Scope Adrenalectomy (MBSA) and the patient had no more evidence of kidney cancer.
If you have been told that your cancer has spread to your adrenal gland(s), this may be something you did not know happened frequently. Unlike the spread of cancer to other areas, such as the liver, spread to the adrenal glands is not talked about as frequently. That said, adrenal metastases are quite common with lung cancer and other cancers. Nearly any cancer can spread to the adrenal glands, but some tumors are more likely than others to metastasize to this region. The cancers that most frequently spread to the adrenal gland(s) are:
- Lung cancer (Primarily non-small cell lung cancer; NSCLC)
- Kidney cancer (Renal cell carcinoma)
- Malignant melanoma
- Breast cancer
- Colon & Rectal cancer
- Stomach cancer (Gastric carcinoma)
- Esophageal cancer
- Liver cancer (Hepatocellular carcinoma)
- Lymphoma
How are Adrenal Metastases Detected?
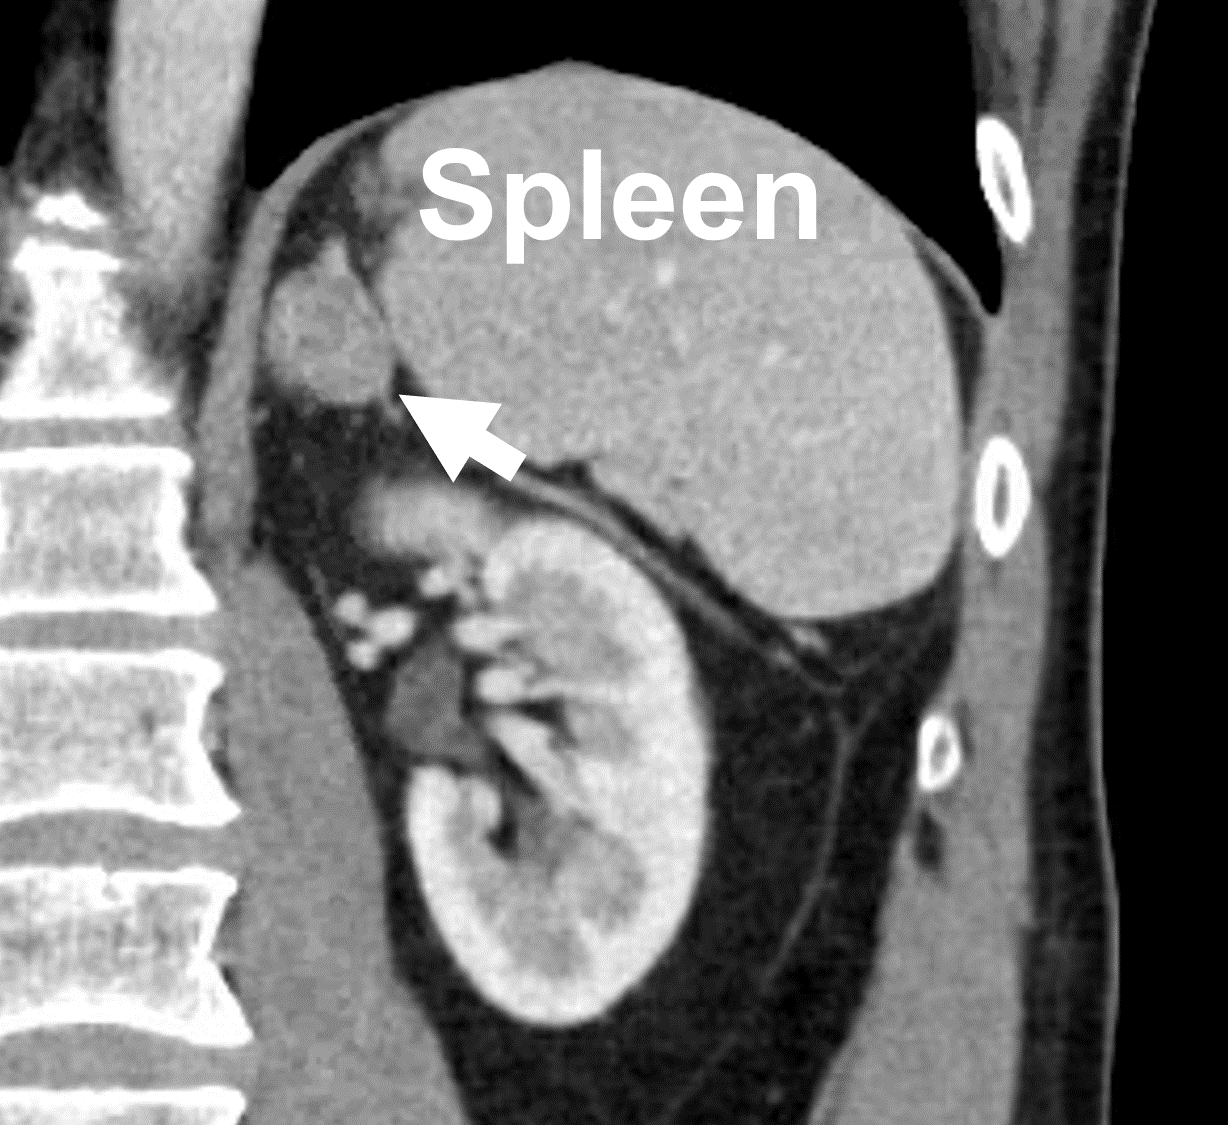 CT scan demonstrating a left adrenal metastasis from colorectal cancer (arrow). Dr. Carling performed a successful partial, adrenal-sparing operation via the Mini Back Scope Adrenalectomy (MBSA) since the patient had a previous right adrenalectomy.
Most adrenal metastases do not cause symptoms. The great majority are detected on a scan, such as a CT, MRI or PET scan, performed before or during treatment for the underlying cancer. Sometimes, an adrenal metastasis is diagnosed due to symptoms, such as back, flank or abdominal pain, bleeding into the tumor, or, rarely, adrenal insufficiency (also called Addison’s disease) if both adrenal glands are destroyed by the cancer.
Not every adrenal mass in a patient with cancer is a metastasis. Many are benign adrenal adenomas, which can be recognized on a non-contrast CT scan (10 Hounsfield units or less), and it is important that a benign adenoma is not mistaken for stage 4 disease. If you have a scan suspicious for adrenal metastases, you do not necessarily need extensive further evaluation, especially if you have metastases to other regions of your body. In some cases, your doctor may wish to be certain that a mass in your adrenal gland is due to metastatic cancer and recommend a CT-guided biopsy. Adrenal biopsy is rarely needed, but a suspected metastasis is the main situation in which it is appropriate. It should never be done before a pheochromocytoma has been excluded with a blood or urine metanephrine test. Read about adrenal mass biopsy here.
Should all Adrenal Metastases be Removed with Surgery?
No. Not all adrenal metastases should be removed. In fact, in most cases, removing adrenal metastases is not helpful because the cancer has spread elsewhere. In such a scenario, systemic treatment with chemotherapy, targeted therapies, immunotherapy, and/or radiation therapy is better. Some people also participate in clinical trials studying new drugs and procedures. However, if you or your loved one has a solitary (single) adrenal metastasis and the original cancer is under control, then complete surgical removal offers the best-established chance of long-term control. Important: the decision to proceed with adrenalectomy for metastatic cancer requires thoughtful consideration of the natural history of the underlying cancer, tumor biology, presence of disease outside the adrenal (if any), patient performance status, and availability of alternative treatments. It is best made together with your oncologist.
Is Radiation or Ablation of Adrenal Metastases as Good as Surgical Removal?
In suitable patients, we believe surgery gives better local control than radiation (stereotactic body radiotherapy; SBRT) or ablation (image-guided percutaneous ablation). The two have not been compared head to head in a randomized trial. SBRT or ablation is a reasonable alternative for patients who are not good candidates for surgery or would not tolerate an adrenal operation.
Can an Adrenal Metastasis be Removed with the Mini Back Scope Adrenalectomy (MBSA)?
Yes, in experienced hands. Many surgeons use a different approach for metastases. The Mini Back Scope Adrenalectomy (MBSA) technique is well suited to patients with adrenal metastases and to disease in both glands, where an adrenal-sparing operation may preserve adrenal function. Very large tumors, or tumors growing into neighboring organs, may need a different approach.
Last updated October 2026.