Do Children and Teenagers Get Pheochromocytomas?
Pheochromocytomas (and paragangliomas) are rare tumors in children and teenagers, but yes, they do occur: about 10–20% of all these tumors are found in children and teenagers. Most of these tumors cause symptoms, which are due to the excess secretion of catecholamines (adrenaline-type hormones). Pheochromocytomas in children typically cause hypertension, palpitations, sweating, and headaches. In children the high blood pressure is more often constant than episodic.
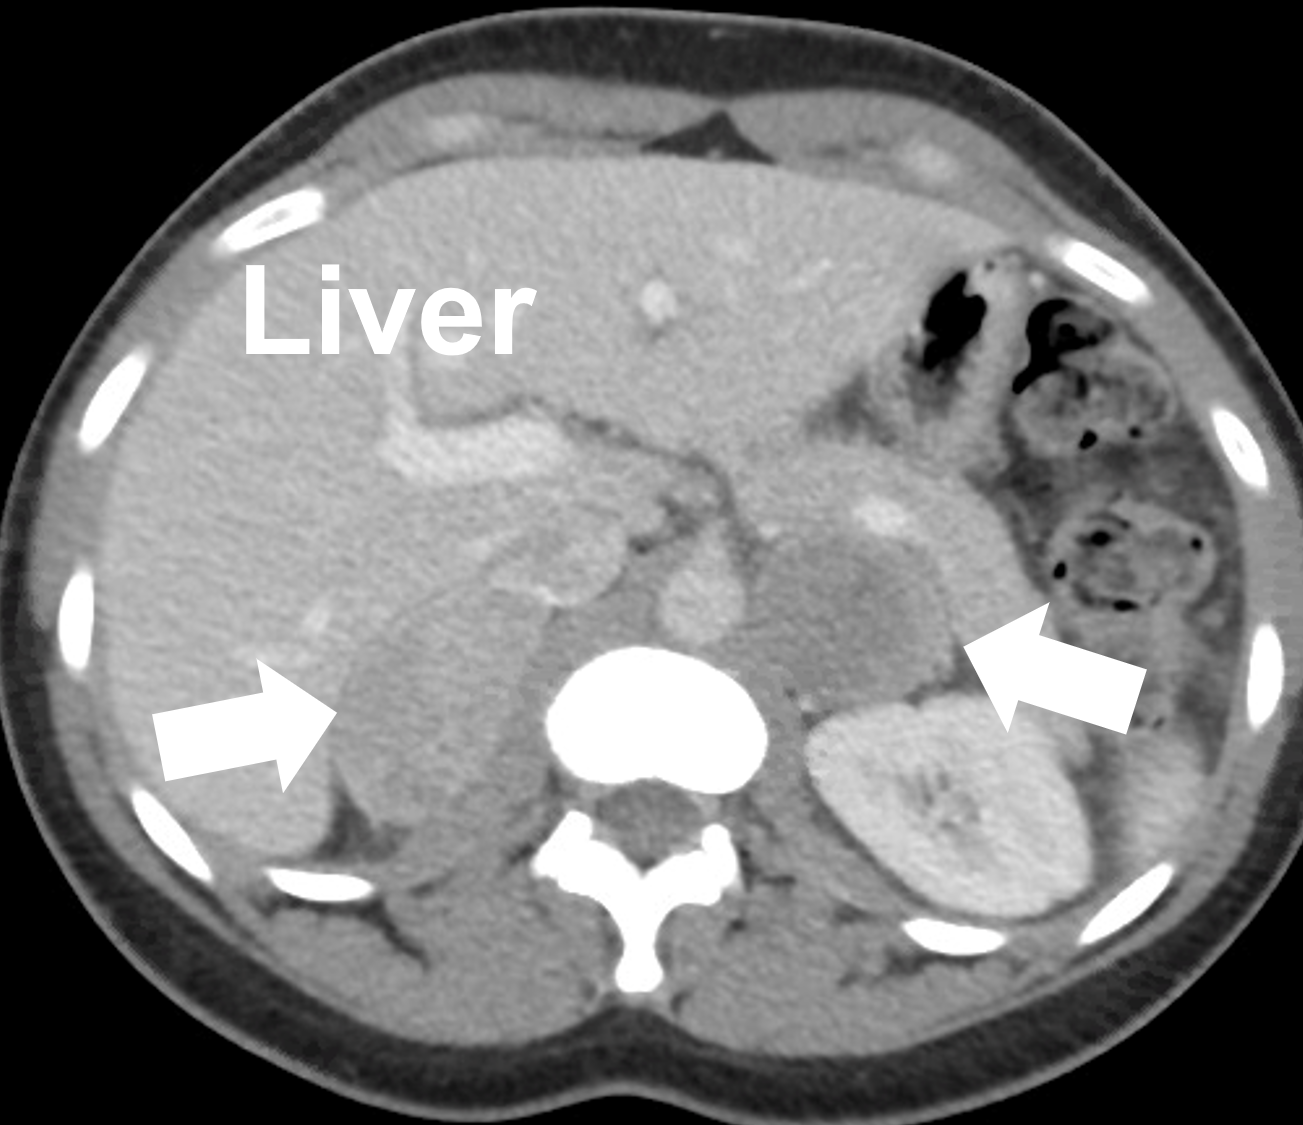 Bilateral (both left and right) pheochromocytomas seen on a CT scan (arrows) in a young patient with inherited pheochromocytomas due to multiple endocrine neoplasia type 2A (MEN2A). The patient underwent successful adrenal-sparing (partial) adrenalectomy via Mini Back Scope Adrenalectomy (MBSA).
Children with High Blood Pressure Should be Checked for Pheochromocytoma.
About 1% of children with high blood pressure have a pheochromocytoma or paraganglioma as the cause. Most pheochromocytomas in children are hereditary: around 70–80% of affected children carry an inherited (germline) change in one of the susceptibility genes, compared with about 30–40% of patients overall. The genes involved (in brackets) include those causing von Hippel–Lindau syndrome (VHL), multiple endocrine neoplasia type 2 (RET), neurofibromatosis type 1 (NF1) and the hereditary paraganglioma syndromes (SDHD, SDHAF2, SDHC, SDHB, SDHA), as well as MAX, FH, and TMEM127. VHL and SDHB are the most common in children. This is why genetic testing and counseling should be offered to every child with one of these tumors, and to the family. Learn more on our pheochromocytoma genetics page.
Are Pheochromocytomas in Children Cancer? Can They Spread?
Pheochromocytomas and paragangliomas are no longer divided into "benign" and "malignant". Most never spread, but every one of these tumors has some potential to spread (metastasize). The risk depends largely on the underlying gene and is highest in patients who carry a change in the SDHB gene. Children also have a higher risk than adults of a tumor coming back or of new tumors forming later in life. This is why genetic testing and lifelong follow-up, with a metanephrine test every year, matter so much for a child with a pheochromocytoma.What is the Best Surgery for Pheochromocytoma in Children?
Surgery is the treatment of choice for pheochromocytoma in children and teenagers. Just as with adults, the Mini Back Scope Adrenalectomy (MBSA; posterior retroperitoneoscopic adrenalectomy) is our preferred technique for most pediatric adrenal operations. Because most of these children have a hereditary condition that can affect both adrenal glands over a lifetime, adrenal-sparing surgery (partial adrenalectomy), which removes the tumor but preserves healthy adrenal tissue, is often the right operation: it can spare a child lifelong steroid dependence. The trade-off is that a new tumor can grow in the remaining adrenal tissue years later, which is another reason follow-up is lifelong. Before surgery, children are prepared with blood-pressure medication and good hydration, just as adults are. Pheochromocytoma in a child is rare enough that most surgeons and hospitals will never see one, so we recommend that these children be treated by an experienced, high-volume team that includes endocrinology, genetics, anesthesia and adrenal surgery. Read more about adrenal surgery in children.
The diagnosis of pheochromocytoma in children hinges on the treating physician thinking about the diagnosis in the first place. The diagnosis is made with one of the following tests, which measure metanephrines (the breakdown products of the adrenaline-type hormones) in the blood or urine:
• Measurement of plasma free metanephrines (metanephrine and normetanephrine; a blood test). This is a very sensitive test. The blood is ideally drawn after the child has been lying down and resting for at least 20 minutes, and the result must be compared with reference ranges for the child's age. A level more than about 3 times the upper limit of normal almost always indicates the presence of a pheochromocytoma or paraganglioma.
• 24-hour collection of urine fractionated metanephrines. This is also an accurate test and can be used instead of the blood test or to confirm it.
For scans, MRI is the appropriate first choice in children because it uses no radiation; see our pheochromocytoma scans page.
Many medications may affect (increase) the test results, so tell us and your doctor what medications (if any) your child was taking while being tested. The list of medications that may interfere with the measurement of metanephrines is on the "Lab Testing" for pheochromocytoma page.
Last updated October 2026.
Become Our Patient
Patients needing adrenal surgery travel from all over the world to have adrenal surgery with Dr. Carling, one of the world's most experienced adrenal surgeons. The link below explains how you can have your adrenal operation at the Carling Adrenal Center with Dr. Carling himself.What to read next
- Mini-Back-Scope-Surgery - our preferred adrenal operation for most adrenal tumors, including most pheochromocytomas in children.
- More about our founder Dr. Tobias Carling - one of the world's most experienced adrenal surgeons.
- How to become our patient, and have Dr. Carling help you understand pheochromocytomas in children and how he may help you with a child needing adrenal surgery.