Surgery for Pheochromocytoma: Adrenalectomy Options, Preparation and Recovery
In our experience, the best adrenal operation for most pheochromocytomas (and thus, likely your pheochromocytoma) is the posterior retroperitoneoscopic adrenalectomy, or more simply put, the Mini Back Scope Adrenalectomy (MBSA). This page explains how patients are prepared for surgery, the operation itself, adrenal-sparing surgery for hereditary disease, and follow-up.
Surgery for Pheochromocytoma (Adrenalectomy)
Surgery to remove the tumor is the treatment for almost all pheochromocytomas. Which operation is right depends on the problem that needs to be fixed. There are several factors that an expert adrenal surgeon will consider in choosing the operation for your pheochromocytoma:
- The size of the tumor (as measured on the preoperative scan: usually a CT scan or MRI, sometimes a specialized nuclear medicine scan)
- Whether the pheochromocytoma is hereditary and whether one or both adrenal glands are involved (this is why genetic testing should be offered to every patient, ideally before surgery: the result can change the operation)
- The appearance of the tumor on the preoperative scan (Is the tumor involving surrounding structures, such as organs or vessels?)
- A history of previous abdominal operations
- The surgeon's experience with the different adrenal operations
Remember that the typical surgeon who performs adrenal surgery does about one adrenal operation per year, and more than 80% of adrenalectomies in the United States are performed by low-volume surgeons. Outcomes are better with surgeons who do it regularly, and this matters even more for pheochromocytoma. We recommend choosing a surgeon and center that operate on pheochromocytomas regularly, even if that means traveling. Dr. Carling has performed thousands of adrenal operations over his career, including more than 2,400 since January 2022 alone, and personally performs every operation.
Preparing for pheochromocytoma surgery
A pheochromocytoma can release large amounts of adrenaline-type hormones during anesthesia and surgery, so preparation matters. Most patients are prepared with blood-pressure medication (alpha-blockers such as doxazosin or phenoxybenzamine, sometimes other medicines) and good hydration before surgery; a beta-blocker, if needed for a fast heart rate, is added only after the alpha-blocker has been started. The plan is individualized by our team. Some pheochromocytomas are “silent”: the patient has normal blood pressure and the tumor is found incidentally on a scan. In our center's published series, about 15% of non-hereditary (sporadic) pheochromocytomas were silent. These tumors still need careful management around the time of surgery.
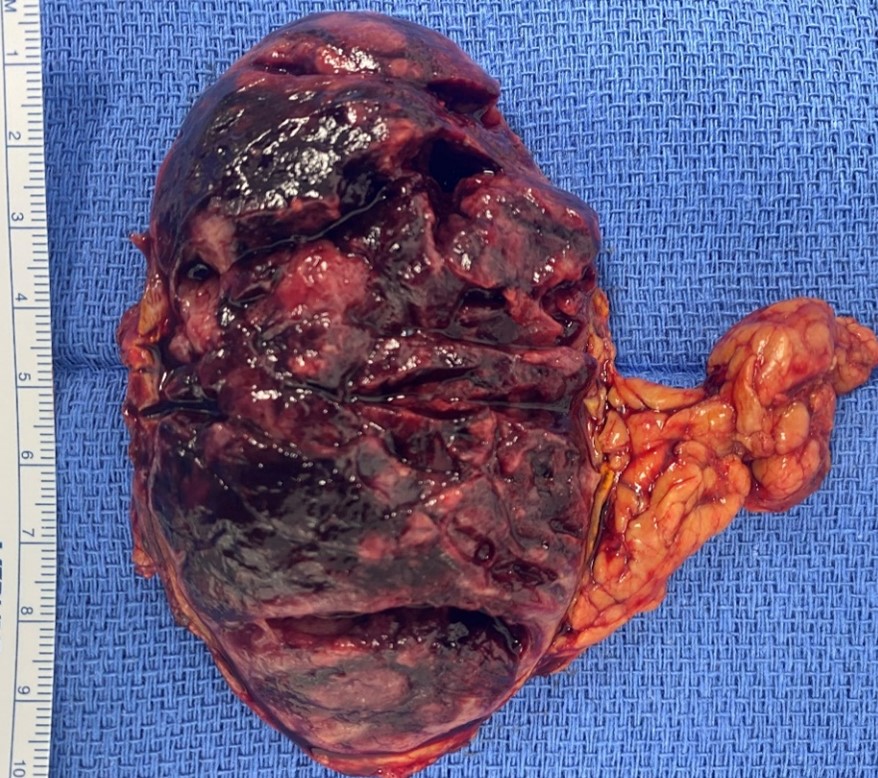 Typical right pheochromocytoma after it was removed by Mini Back Scope Adrenalectomy (MBSA) by Dr. Carling. The tumor was large and produced massive amounts of adrenaline-type hormones. The tumor is dark. Pheo = dark (ancient Greek), chromo = color, cytoma = cell tumor
The Mini Back Scope Adrenalectomy (MBSA) is the best adrenal operation for most pheochromocytomas
Since the adrenal glands live in the back part of your abdomen, sitting on top of the kidneys, getting to them through the back with small scopes makes the most sense and has several advantages. We use the MBSA for more than 95% of our operations.
Read more about the advantages of the Mini-Back-Scope Adrenal Operation.
With the way the Mini Back Scope Adrenalectomy (MBSA) operation is done, particularly when performed by an expert adrenal surgeon, blood loss is usually minimal. By going through the back, the scopes are placed directly into the space where the adrenal glands are located, so less mobilization (i.e., dissection of surrounding structures) is needed. Less dissection means less blood loss and less risk of injury to surrounding structures (such as the kidney, liver, spleen, pancreas, and bowel) or major vessels (such as the inferior vena cava). Furthermore, less dissection leads to fewer postoperative adhesions (scar tissue).
In experienced hands the MBSA is also a fast operation, about 20 minutes, since again, the scopes are placed directly into the space where the adrenal glands are. This is important in every surgery, but in particular in an adrenal operation for pheochromocytoma. A shorter operation means less time under general anesthesia and less opportunity for the blood pressure and heart rate fluctuations that can be extreme during an operation for pheochromocytoma. It also takes an anesthesia and nursing team that looks after pheochromocytoma patients regularly.
 Dr. Carling and his team are focusing during a Mini Back Scope Adrenalectomy (MBSA) for pheochromocytoma.
When performing Mini Back Scope Adrenalectomy (MBSA) for pheochromocytoma, the surgeon does not need to enter the belly. This is a clear advantage for those with previous abdominal operations, since the surgeon does not need to contend with adhesions (scar tissue). Intra-abdominal adhesions may result from any previous belly operation such as bariatric surgery (gastric band, sleeve gastrectomy, gastric bypass), gallbladder surgery (cholecystectomy), liver surgery, stomach surgery, bowel surgery of any kind (colectomy, appendectomy, etc.), trauma surgery, or any gynecological operation (C-section, hysterectomy, etc.). By approaching your pheochromocytoma through the back, your surgeon will not encounter the bowel, and the operation does not create new scar tissue inside the abdomen. Scarring near the bowel can lead to small bowel obstruction, a complication that can occur at any time after belly surgery.
Since the MBSA requires less dissection and a shorter operating time, there is less postoperative pain and a quicker recovery. Many patients only require Tylenol (acetaminophen) or Motrin (ibuprofen) after the operation. Very few patients need strong painkillers, which have their own negative side effects.
Recovery after adrenalectomy for pheochromocytoma
After an uncomplicated MBSA, most patients spend one night (less than 23 hours) in the hospital. After a pheochromocytoma is removed, blood pressure and blood sugar can drop, so both are monitored closely in the first hours. Most people return to work within a few days, and you can typically resume your hobbies and exercise within the week following MBSA. The cosmetic result is excellent: three small incisions, each less than a thumbnail in length.
Adrenal-sparing surgery for hereditary and bilateral pheochromocytoma
About 30–40% of pheochromocytomas are hereditary, and in hereditary syndromes such as MEN2 and von Hippel-Lindau (VHL) disease the tumors often affect both adrenal glands, at the same time or years apart. Removing both adrenal glands completely removes the pheochromocytomas but leaves the patient dependent on steroid medication for life, with a lifelong risk of adrenal crisis. For these patients we favor adrenal-sparing surgery (partial adrenalectomy) whenever it is appropriate: the tumor is removed while enough healthy adrenal cortex is preserved to keep making cortisol. The operation is tailored to each patient; the options range from adrenal-sparing surgery on one or both sides to total removal of one gland with adrenal-sparing surgery on the other.
The honest trade-off is recurrence. In the largest international registry of patients with bilateral pheochromocytoma, about 13% of patients who had adrenal-sparing surgery developed a new pheochromocytoma in the remaining adrenal tissue, usually many years later; these recurrences can be treated with another operation. This is why lifelong follow-up is essential. Adrenal-sparing surgery is not right for everyone, for example when the inherited gene carries a high risk of metastatic disease. For patients who need surgery on both sides, the MBSA has the advantage that there is no moving and turning of the patient during the operation to reach the two adrenal glands. Read more about adrenal-sparing surgery.
When is another operation needed?
We believe the Mini Back Scope Adrenalectomy (MBSA) is the best adrenal operation for most patients requiring pheochromocytoma removal. The MBSA suits most tumors; very large tumors, or tumors known or suspected to have invaded surrounding structures or to have spread, may need a different approach. Ask your surgeon which approaches they offer and why. Pheochromocytoma surgery is planned surgery, not emergency surgery: you need time to be prepared with medication first, which also gives you time to seek an expert surgical opinion. But a pheochromocytoma is dangerous while it remains in place, so do not delay beyond that.
For those whose tumor size or characteristics do not allow for an MBSA, there are still good options available. However, you should be prepared for more pain after the operation, a longer hospital stay and recovery, and a slower return to work and your normal activities and exercise.
The other approaches to pheochromocytoma are as follows:
Laparoscopic trans-abdominal adrenalectomy, laparoscopic hand-port assisted trans-abdominal adrenalectomy, and standard open adrenalectomy. Open surgery remains appropriate for very large tumors and for tumors that invade surrounding structures.
Read about the different approaches to adrenal surgery. Remember, not all “minimally invasive” adrenal operations for pheochromocytoma are created equal. Read why we prefer the back approach in our blog post on laparoscopic adrenalectomy.
Your adrenal operation for pheochromocytoma should be dictated by your specific circumstances, since one operation does not fit all tumors. If your surgeon is not comfortable with the different techniques, including MBSA and adrenal-sparing surgery, you should consider a second opinion. A customized, individual approach to your pheochromocytoma gives the best chance of a good outcome.
Laparoscopic Hand-port Assisted Trans-Abdominal Adrenalectomy is used for the few pheochromocytomas that are very large
This approach is a hybrid between laparoscopic transabdominal adrenalectomy (LTA) and open standard trans-abdominal adrenalectomy. The positioning of the patient and the approach are similar to those of the laparoscopic transabdominal adrenalectomy (LTA). This approach is for very large tumors and for tumors that appear to involve surrounding structures.
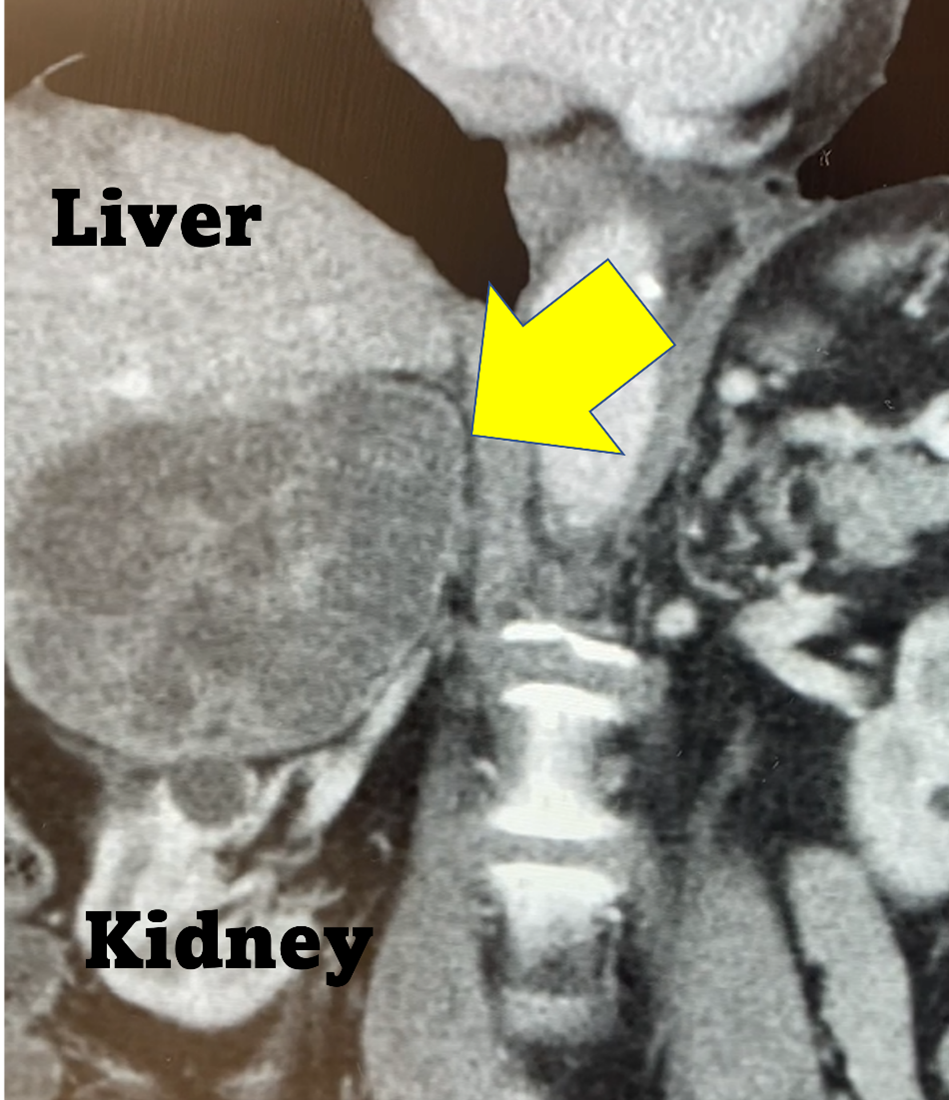 Very large 15 cm right pheochromocytoma on a CT scan. This pheochromocytoma is better removed using the Laparoscopic Hand-port Assisted Trans-Abdominal Adrenalectomy.
After surgery: lifelong follow-up
Removing the tumor removes the source of the excess hormones, but every pheochromocytoma has some potential to spread or come back, and new tumors can form, sometimes many years later. Everyone who has had a pheochromocytoma therefore needs lifelong follow-up with a metanephrine test every year.
Pheochromocytoma is sometimes associated with a specific type of thyroid cancer (medullary thyroid cancer) and with parathyroid tumors, in the inherited syndrome multiple endocrine neoplasia type 2 (MEN2).
Learn more about thyroid disease, thyroid cancer and thyroid surgery.
Learn more about parathyroid disease and parathyroid surgery.
Last updated October 2026.