What is Adrenal Cancer?
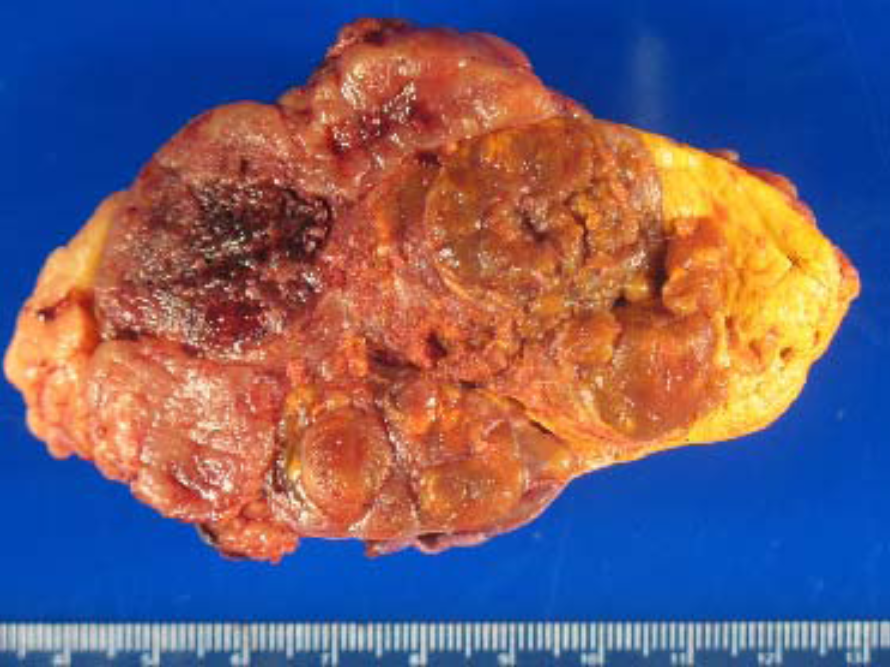 A typical 10 cm adrenal cancer demonstrating irregular borders, invasion, and areas of necrosis (dead cells) and hemorrhage (bleeding).
Adrenal cancer (or adrenocortical carcinoma; ACC) is a relatively rare but aggressive cancer. The only potential cure is complete surgical removal. Adrenal cancer is most often diagnosed in adults between 40 and 60 years of age, with a second, smaller peak in early childhood, but it can occur at any age. It is potentially curable when it is found while still confined to the adrenal gland. Unfortunately, these tumors grow fast, and many are found only after they have grown into nearby tissues and organs (local invasion) or have spread to distant organs such as the lungs, liver and bone (metastasis). These are two different situations: a tumor that has invaded locally may still be removed completely, whereas distant metastasis usually cannot be cured by surgery alone. Adrenal cancers can also cause numerous changes (signs and symptoms) in the body because of the excess hormones they produce. Note: when we talk about adrenal cancer, we mean adrenocortical carcinoma, which arises from the adrenal cortex. Tumors arising from the adrenal medulla are pheochromocytomas; one that has spread is called a metastatic pheochromocytoma. Read about pheochromocytoma.
Adrenocortical carcinoma is an aggressive cancer with a serious prognosis. Again, complete surgical resection offers the sole chance for potential cure. Adrenal cancer surgery should be done by a surgeon and a center with specific experience in it, because the first operation is the best chance of cure. Given that adrenal cancer is rare, there have been international efforts to improve the care of adrenal cancer patients. Dr. Carling is very much part of these efforts to enhance collaboration and to understand the basis (molecular genetics) of adrenal cancer formation. These genetic studies have identified factors that may be used in the diagnosis and to predict treatment response. The Carling Adrenal Center created this website to educate both patients and health care providers, including other doctors, about adrenal cancer. We strongly believe that educated patients are much better equipped to face the challenges of overcoming adrenal cancer.
What are the characteristics of Adrenal Cancer?
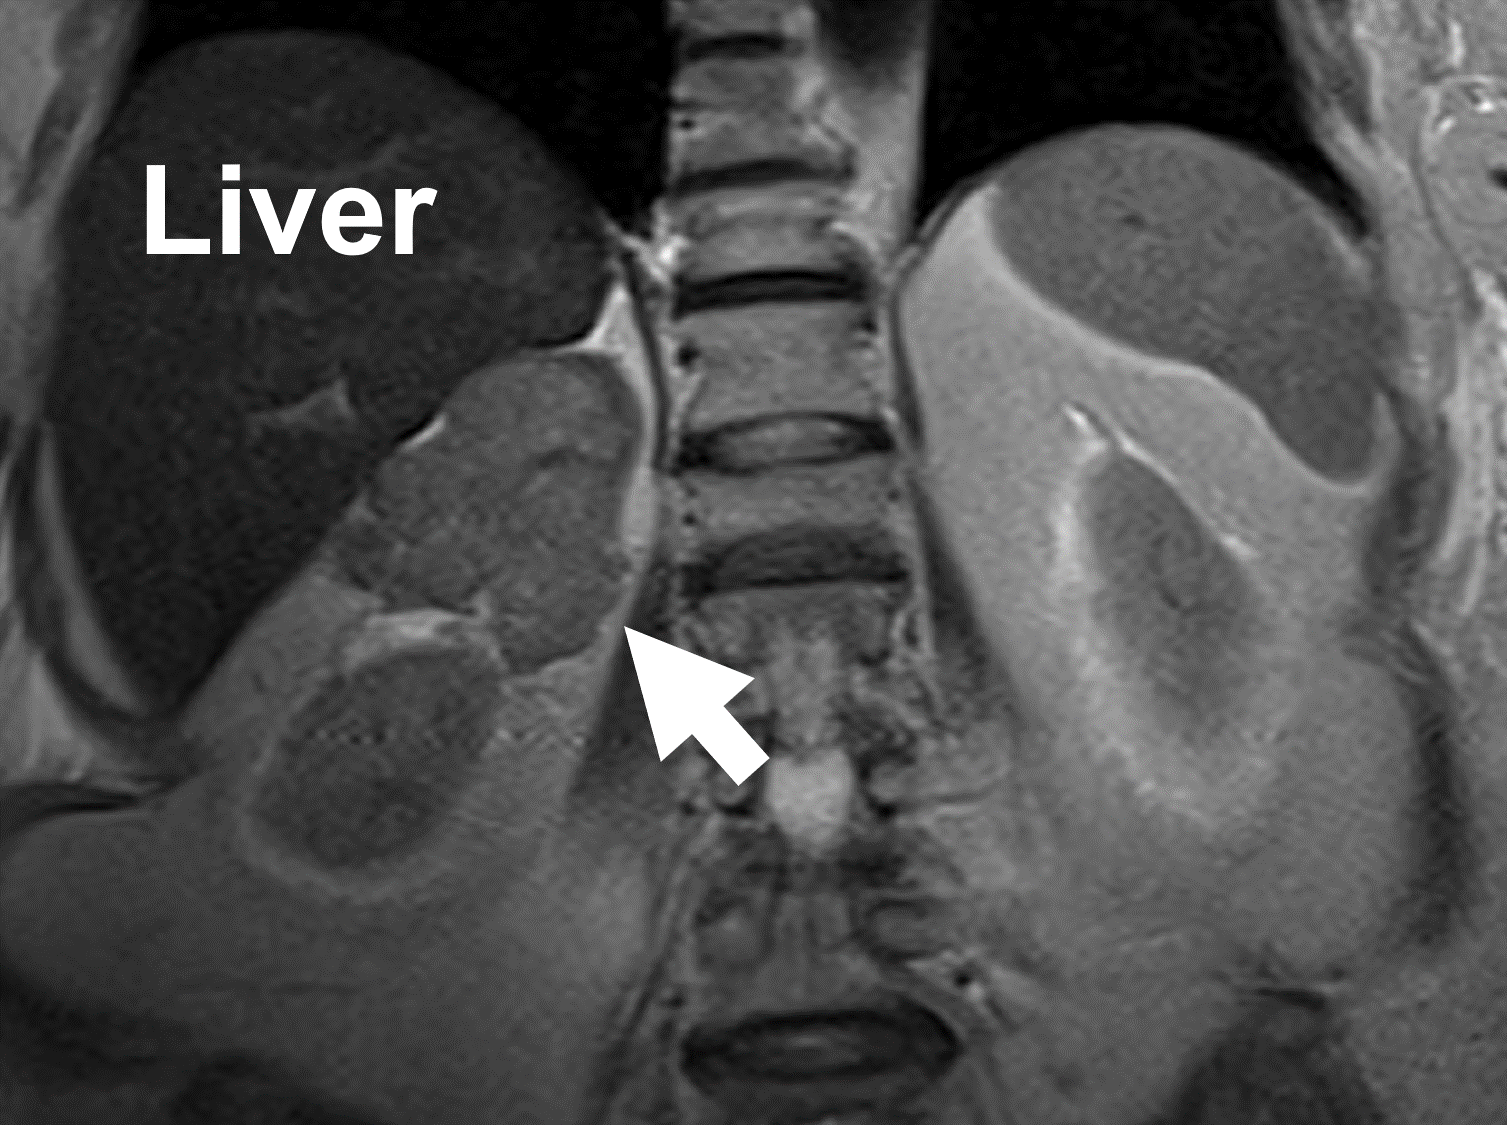 MRI showing an adrenal cancer (arrow) arising from the right adrenal gland. Note the heterogeneity and irregular borders. This tumor overproduced cortisol, causing severe adrenal hypercortisolism (Cushing syndrome).
- Typically adrenocortical carcinoma is an aggressive cancer
- About half or more make too much of one or more adrenal hormones, most often cortisol, with or without androgens (male-type hormones), and are found because the hormone excess causes symptoms which prompt patients to seek medical attention
- Others are found because of pain or fullness in the abdomen and flank from a large tumor, and a growing number are found by accident on a scan done for another reason
- Spread to distant organs (metastasis) occurs most commonly to the lungs, liver, and bone
- The initial evaluation should include blood and urine tests to measure adrenal hormones. Since many of these cancers make too much hormone (cortisol, testosterone, estrogen, other androgens, DHEA-S, aldosterone, etc.), this is an obvious place to start; see laboratory tests for adrenal tumors. Keep in mind, however, that many non-cancerous tumors of the adrenal glands (benign adenomas) also secrete too much hormone. Therefore, demonstrating overproduction of adrenal hormones does not by itself distinguish between benign and malignant (cancerous) tumors. Very high levels, a tumor making both cortisol and sex hormones, and symptoms that come on quickly are all more typical of a malignant tumor.
- Scans play a central role in the diagnosis of adrenal cancers and in determining the type of treatment planned. Computed tomography (CT) and/or magnetic resonance imaging (MRI) of the abdomen are the central tests. A CT scan of the chest and often a PET scan (FDG-PET) are added to look for spread, which determines the stage. Read more about scans for adrenal tumors.
- A needle biopsy is not recommended when a tumor is suspected to be an adrenal cancer that can be removed: it cannot reliably tell a benign from a malignant adrenal tumor and risks spreading tumor cells. Read more about the risk of cancer and adrenal biopsy.
- Many patients will seek medical attention because of a bodily change that typically comes on quickly, over weeks to months. Rapid onset of hormone symptoms is a warning sign of adrenal cancer; changes that develop slowly over years are more typical of a benign tumor. When excess female hormones are produced in a female it can be hard to detect, except at extremes of age such as early puberty in a child, or the return of vaginal bleeding in a post-menopausal woman. The same is true for excess testosterone in a male. The opposite, however, will often make the presentation obvious, such as when a woman begins to develop male characteristics (deeper voice, excess body hair) or when a man begins to develop enlarged breasts (gynecomastia). Some of these hormone overproduction problems have specific names:
- Severe adrenal hypercortisolism (AHC), also called adrenal Cushing syndrome (excess cortisol produced)
- Virilization (acquisition of male traits in a female because of excess testosterone production)
- Feminization (acquisition of female traits in a male because of excess estrogen production)
- Precocious puberty (puberty occurring too early because of excess sex steroids produced)
- Primary aldosteronism (excess aldosterone leading to hypertension and low potassium; rare in adrenal cancer)
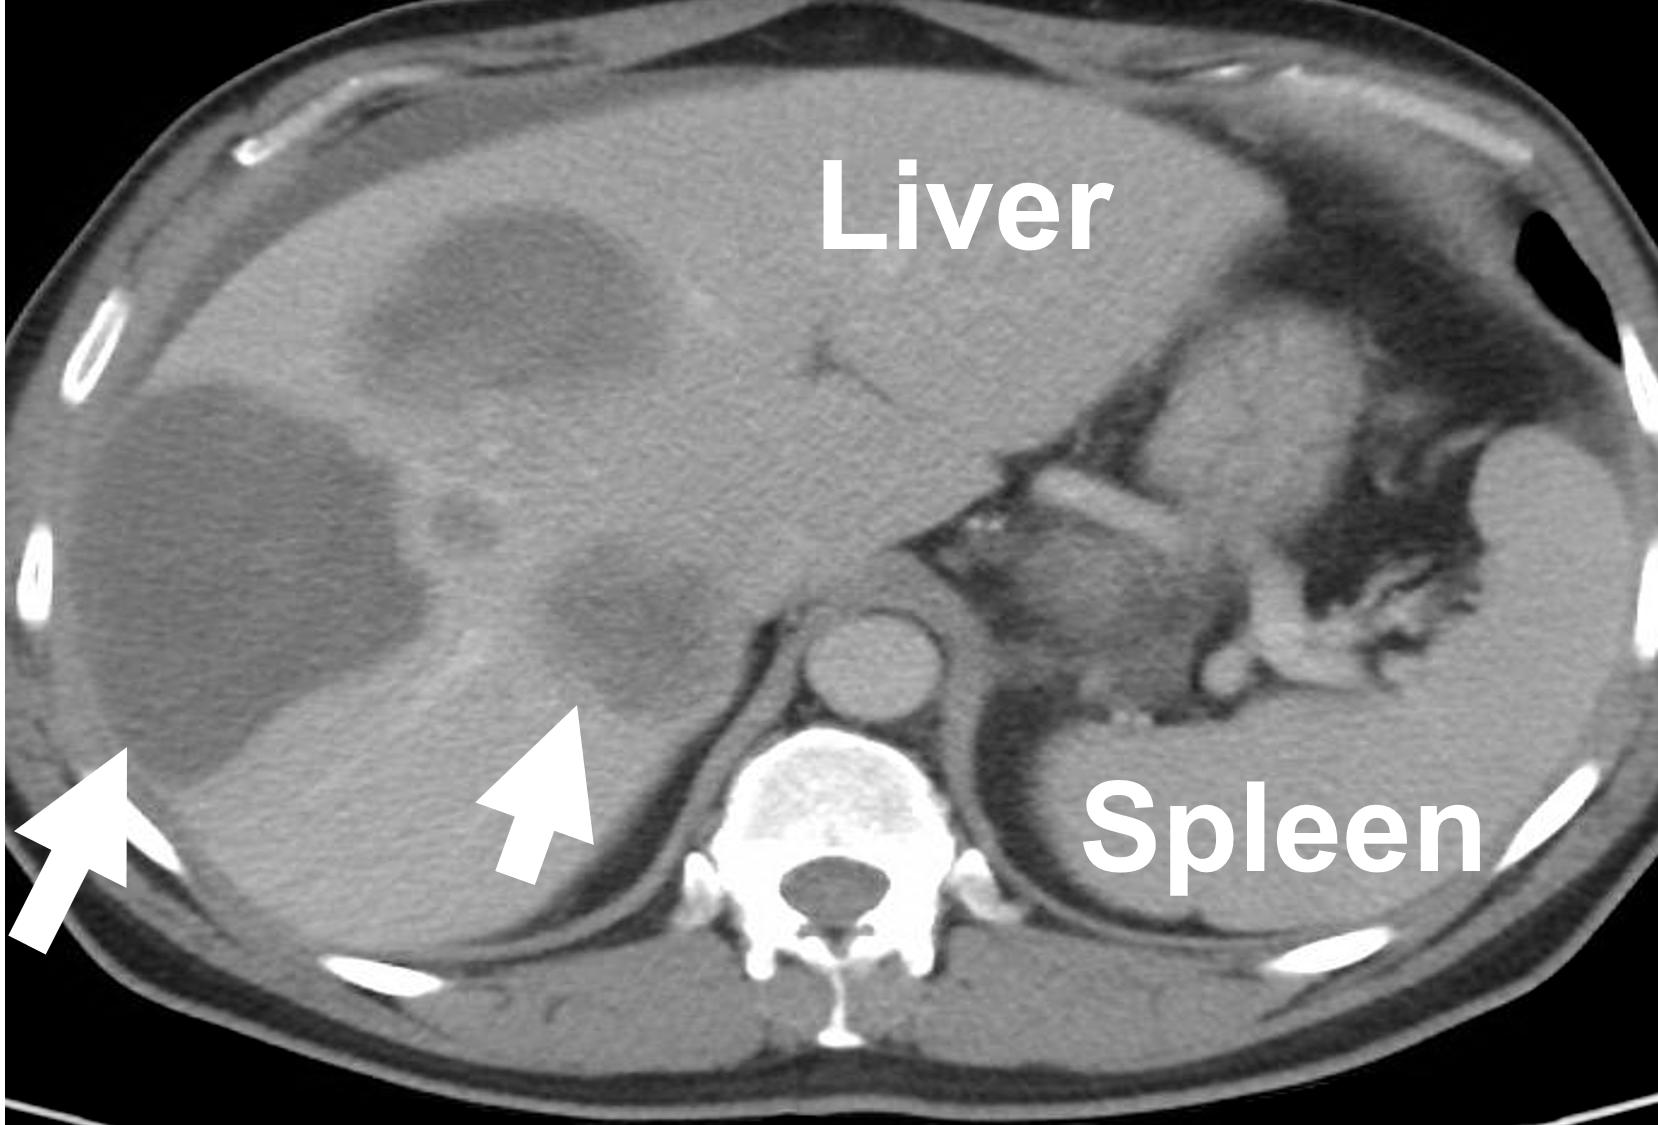 CT showing liver metastases (arrows) from an adrenal cancer arising in the adrenal gland. This tumor overproduced estrogen causing feminization (acquisition of female traits in a male).
How is Adrenal Cancer Staged and Treated?
Staging. Adrenal cancer is staged with the ENSAT system, from stage I to stage IV. Stage I is a tumor of 5 cm or less confined to the adrenal gland. Stage II is a tumor larger than 5 cm that is still confined to the gland. Stage III means the tumor has grown into surrounding tissues, nearby lymph nodes or the large veins. Stage IV means it has spread to distant organs. The stage, and whether the tumor could be removed completely, matter most for the outlook.
Surgery. Complete removal of the tumor in one piece, without breaking its capsule, is the only potential cure. Open surgery by an experienced team is the standard for known or suspected adrenocortical carcinoma, often together with removal of the nearby lymph nodes. Our Mini Back Scope Adrenalectomy (MBSA) suits most adrenal tumors, but very large tumors and known adrenal cancers may need a different approach. Read about open adrenal surgery.
Mitotane and other treatments. Mitotane is a medication used after surgery (adjuvant therapy) in selected patients with a higher risk of the cancer coming back, and as systemic therapy, alone or together with chemotherapy, when the cancer cannot be removed or has spread. Mitotane also shuts down the body's own cortisol production, so patients taking it need steroid replacement and close monitoring. Because some adrenal cancers are hereditary, genetic counseling should be offered, and every patient needs regular follow-up scans after surgery.
Fortunately adrenocortical cancer (ACC) and metastasis to the adrenal gland are relatively rare. Please use the navigation tools or even the "search" button to locate anything you want to know about the adrenal glands.
Last updated October 2026.