Adrenal Surgery Can Be Performed 8 Different Ways Depending on the Tumor and the Experience of the Surgeon
Adrenal surgery can be performed eight different ways. Which one is best for you depends on your tumor, but which one you are offered also depends on the experience of your surgeon. You must do your homework! Here we provide an overview of the 8 very different surgical techniques a surgeon can use to remove an adrenal gland or adrenal gland tumor, with our view of the pros and cons of each.The typical surgeon who performs adrenal surgery does about one adrenal operation per year, and more than 80% of adrenalectomies in the United States are performed by low-volume surgeons. Outcomes are better with surgeons who do the operation regularly. Please choose your adrenal surgeon wisely, and ask any surgeon how many adrenalectomies he or she performs each year.
The 8 Techniques for Adrenal Surgery: Pros and Cons
#1) Mini Back Scope Adrenalectomy (MBSA). Posterior Retroperitoneoscopic Adrenalectomy.
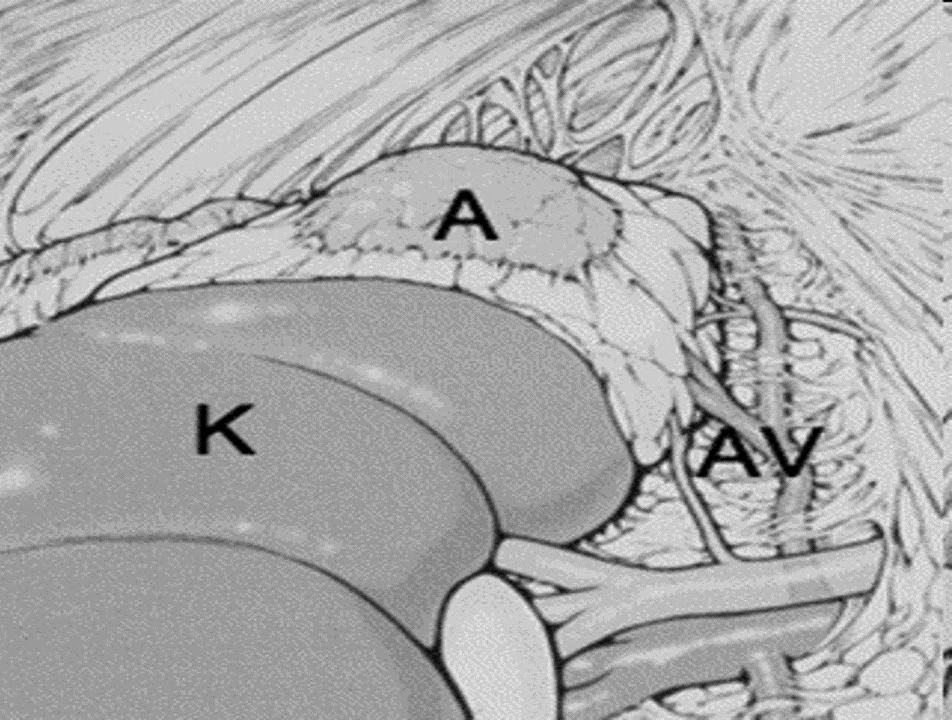 The view of the retroperitoneal space during a left Mini Back Scope Adrenalectomy (MBSA). K = kidney, A = adrenal, AV = left adrenal vein and artery.
This minimally invasive adrenal operation is performed with 1 small scope port placed through the lower part of the patient's back, and 2 other small instrument ports on the sides of the lower back (because the adrenal glands are in the very back of the abdomen). Thus, we refer to this operation as the Mini Back Scope Adrenalectomy (MBSA).
In our view the MBSA is preferable for the vast majority of adrenal tumor patients. It uses an endoscope and very small incisions (0.5-1.1 cm; less than 1/2 inch) and never enters the abdominal cavity. The MBSA is our preferred operation, used for more than 95% of our adrenal operations.
For most small, benign tumors we believe the back approach is the better choice; if your surgeon recommends a different one, ask why. The MBSA typically takes Dr. Carling 20 to 30 minutes to complete. It has limits: the patient lies face down (prone), which does not suit everyone; body build matters (the distance from the skin to the adrenal gland is more important than body mass index, BMI); and very large tumors or known adrenal cancers may need a different approach. We have two entire pages dedicated to the Mini Back Scope Adrenalectomy (MBSA), and its benefits. It is also our preferred technique for adrenal-sparing (partial) adrenalectomy.
#2) Laparoscopic Trans-Abdominal Adrenalectomy (LTA). This is a laparoscopic operation (a laparoscope is a long, thin scope connected to a small high-definition camera) that goes through the front or side of the abdomen. This is the approach most surgeons learn in training, and it is by far the most commonly performed adrenal operation, in the United States and worldwide, including at many high-volume centers. It can be done well by an experienced surgeon. In our view, though, it is not the best adrenal operation for most patients. Dr. Carling uses this method for only a small minority of the adrenal operations he performs each year. If it is offered to you for a small tumor, ask how many adrenal operations your surgeon does each year and whether a back approach is an option.
The most commonly performed adrenal operation is the laparoscopic operation that goes through the front of the abdomen. Published comparisons favor the approach through the back for operating time, pain and length of hospital stay, with similar complication rates. We believe the best operation for most adrenal tumor patients is the Mini Back Scope Adrenalectomy (MBSA) through the patient's back.
The laparoscopic transabdominal operation allows small to moderately sized tumors to be removed using scopes and small incisions. It is well tolerated and is a true "minimally invasive adrenal surgery". Compared with the MBSA, in most comparative studies patients have somewhat more pain after the operation, longer hospital stays and a slower return to work and normal activities.
Why do we prefer the back approach to laparoscopic and robotic adrenalectomy through the belly? Read more on our adrenal surgery blog

#3) Laparoscopic Hand-Port Assisted Trans-Abdominal Adrenalectomy.
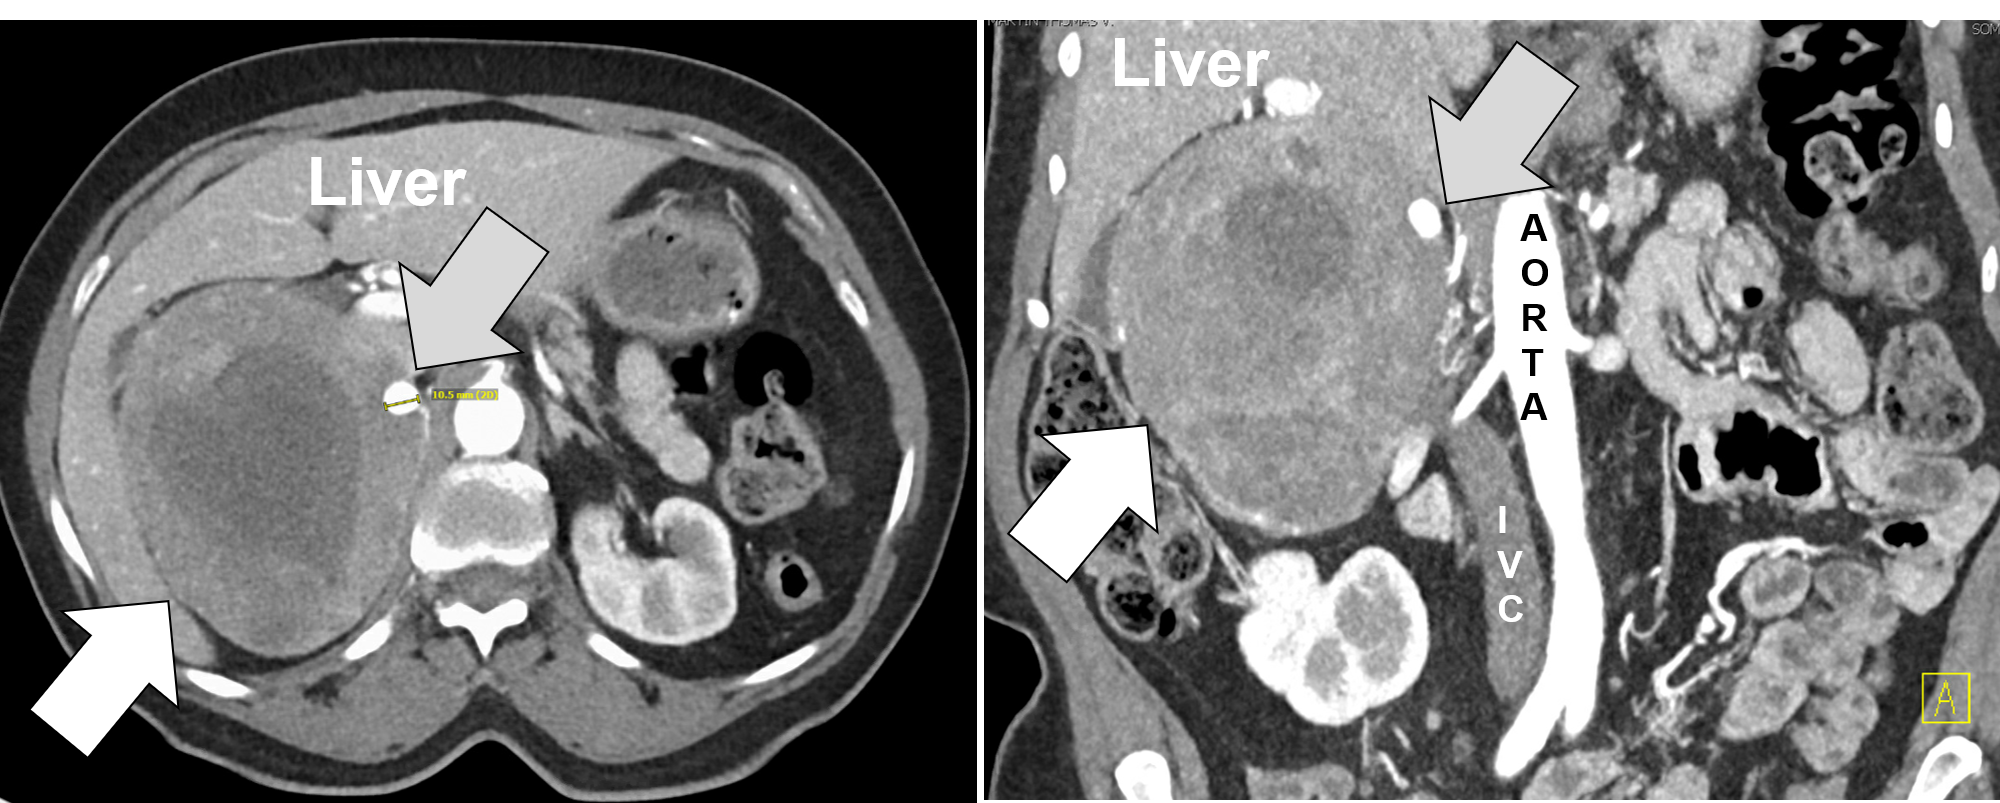 A huge right pheochromocytoma resected by Dr. Carling via Laparoscopic Hand-Port Assisted Trans-Abdominal Adrenalectomy. On the CT scan, the white arrow delineates the 15 cm right adrenal mass. The gray arrow demonstrates a 1 cm intra-tumoral pseudoaneurysm which occasionally occurs in pheochromocytomas.
This surgical technique is a hybrid between laparoscopic transabdominal adrenalectomy (LTA) and open standard trans-abdominal adrenalectomy. The positioning of the patient and the approach are similar to those of the LTA, but one incision is large enough for the surgeon's hand. This approach is appropriate for selected very large tumors, including very large pheochromocytomas. It may also be used depending on the patient’s body habitus. Dr. Carling uses it for some patients with very large adrenal tumors; when adrenal cancer is known or suspected, and especially when the tumor is invading nearby structures, he chooses an open operation instead (see #4). This operation is not the preferred method to remove small adrenal tumors, which make up the large majority of adrenal masses.
#4) Open Standard Trans-Abdominal Adrenalectomy. In this adrenal operation, the surgeon approaches the adrenal glands through an incision on the anterior abdominal wall. Think of this as the traditional operation, where a large incision (usually about 10 inches) is made and the surgeon moves the bowel and other organs out of the way to gain access to the kidney and adrenals.
Open adrenalectomy remains the standard operation for adrenal tumors that are known or suspected to be malignant (cancerous) and for very large tumors, especially if the tumor is invading surrounding structures such as the kidney, liver, spleen, pancreas, bowel, or major vessels such as the inferior vena cava (IVC). For adrenal cancer it gives the best chance of removing the tumor completely and intact. Dr. Carling uses this operation for these large or cancerous adrenal tumors. If your surgeon is planning an open operation for a small, benign-appearing tumor (less than 3 cm), ask why, and consider a second opinion.
#5) Open Thoraco-Abdominal Adrenalectomy. This option allows the greatest exposure of the adrenal gland and all the surrounding structures and therefore is only used for the very largest adrenal tumors. The technique entails making a large incision that crosses both the abdominal and thoracic (chest) cavities, including part of the diaphragm that separates them. This large operation is reserved for the largest and most aggressive cancers of the adrenal gland, to provide adequate exposure of the tumor and its blood supply and allow a complete resection, particularly when the tumor is invading surrounding structures such as the kidney, liver, spleen, pancreas, bowel, or major vessels such as the inferior vena cava (IVC).
#6) Open Posterior Adrenalectomy. The open posterior approach gains access to the adrenal gland through an incision in the back overlying the top of the kidney. This operation is now mostly of historical interest since the introduction of the Mini Back Scope Adrenalectomy (MBSA).
#7) Open Retroperitoneal Adrenalectomy. The open retroperitoneal technique reaches the adrenal gland from behind the abdominal cavity through a large incision in the flank or back, without scopes. This operation, too, is now mostly of historical interest since the adoption of scope operations such as the MBSA, and it is rarely the right choice today.
#8) Robotic (Robot-Assisted) Adrenalectomy. Robotic adrenal surgery uses a surgical robot to expose and remove the adrenal gland. It was first reported around 2000 and is now widely performed. The approach is similar to laparoscopic trans-abdominal adrenalectomy (LTA), or less often to the back approach, except that the surgeon controls the scope and dissecting instruments through a robotic system from a console instead of holding the instruments in his or her hands. Surgeons who use the robot for other operations often prefer it for the adrenal as well, and it can be done well by an experienced team. But in our view it is not the preferred way to remove an adrenal tumor: the robot adds operating time and cost, and no randomized trial has shown that it improves the outcomes that matter to patients compared with standard laparoscopic or back-approach adrenalectomy.
It is possible that robotic surgical systems will become smaller, less expensive and less cumbersome in the future, and we follow their development. For now, we do not perform and do not recommend robot-assisted adrenalectomy at the Carling Adrenal Center. Whatever the tool, the surgeon's experience with adrenal surgery matters most.
What do patients worry about when it comes to adrenal gland removal? Read more on our adrenal surgery blog
What Adrenal Operation is Best for Me?
The best adrenal operation depends on the problem that needs to be fixed. Since most patients with adrenal tumors have a small tumor that is not cancerous, we believe the best adrenal operation for most people is the Mini Back Scope Adrenalectomy (MBSA), also called "posterior retroperitoneoscopic adrenalectomy". There are a number of factors that an experienced adrenal surgeon will consider to determine which adrenal operation is right for a particular patient:- The size of the tumor
- The type of adrenal tumor
- The appearance of the tumor on a CT, MRI, PET or other imaging study, and whether cancer is suspected
- A history of previous abdominal operations
- The patient's body build and ability to lie face down (prone)
- The surgeon's experience with different operations
Please do your homework before you have adrenal surgery. Most surgeons who perform adrenal surgery do it only occasionally, and a surgeon will naturally offer the operation he or she knows best, which is not necessarily the operation that is best for you. Ask how many adrenal operations your surgeon performs each year, and read our page on choosing an adrenal surgeon. If you came this far and somebody you know needs an adrenal operation, the next page for you to read is:
- All the benefits of the Mini Back Scope Adrenalectomy (MBSA) and why we believe it is the best adrenal operation for most people with adrenal tumors.
Last updated October 2026.