Is it Possible to Remove Only Part of the Adrenal Gland?
Yes. There are several circumstances where it is preferable to remove just the adrenal tumor without removing all of the normal adrenal gland with it. This is called adrenal-sparing adrenalectomy, or partial adrenalectomy. The goal is to leave enough normal adrenal tissue behind to avoid adrenal insufficiency (not making enough adrenal hormones). A patient who has both adrenal glands completely removed must take adrenal hormone replacement (steroids) every day for the rest of his or her life and is at risk of a dangerous adrenal crisis during illness. If the surgeon can preserve some normal adrenal tissue with its blood supply, the patient may not need to take any adrenal hormones.
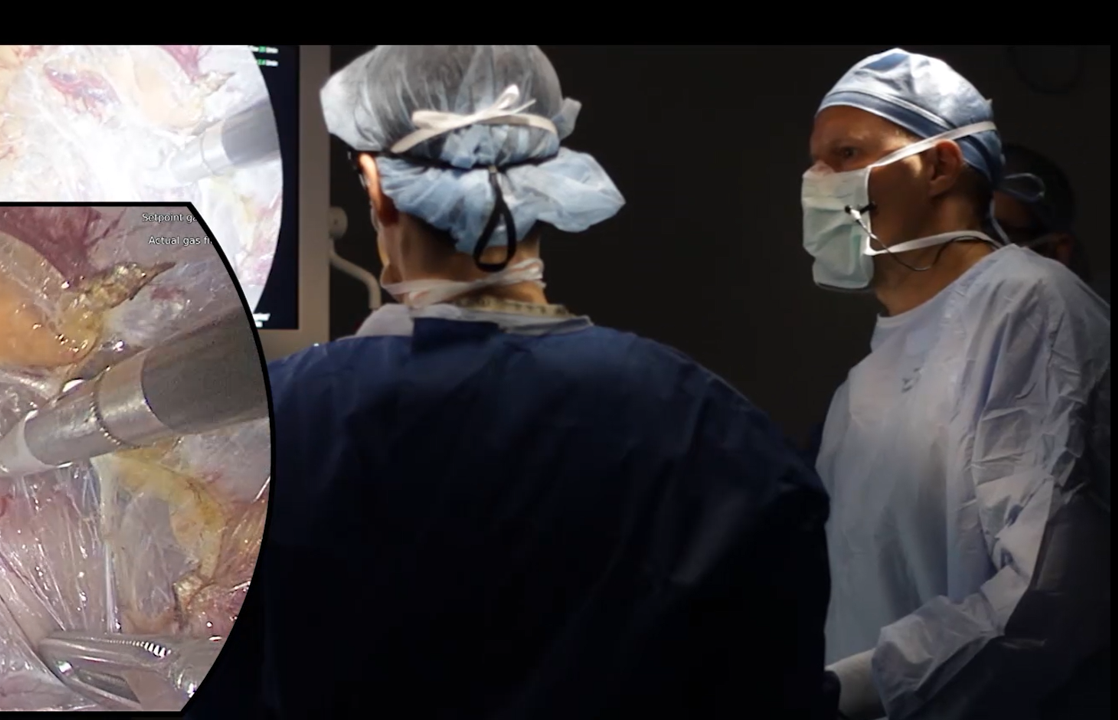 Dr. Carling performing a bilateral adrenal-sparing Mini Back Scope Adrenalectomy (MBSA) in a young patient with familial bilateral pheochromocytoma.
You only need about one-third of one adrenal gland to live normally without taking steroid medication every day. So when one whole gland is removed and the other gland is healthy, most patients do very well. But adrenal-sparing surgery is not only for patients with tumors in both glands. We consider it in several situations:
- Tumors in both adrenal glands, whether from primary aldosteronism (PA), adrenal hypercortisolism (AHC; formerly called MACS or subclinical Cushing syndrome) or pheochromocytoma.
- Hereditary pheochromocytoma (for instance MEN2 or VHL), where a tumor may develop in the other gland years later.
- A solitary remaining adrenal gland, when the other gland was removed in the past.
- Selected patients with a tumor in one gland, when preserving healthy tissue makes sense, for example because the other gland is not entirely normal.
When is an Adrenal-Sparing (Partial) Adrenalectomy Appropriate?
Whether an adrenal-sparing adrenalectomy can be performed depends on four things:- What type of tumor the patient has. Adrenal-sparing surgery should be avoided when cancer is known or suspected.
- The size of the tumor, as well as its relationship to the adrenal vein, surrounding organs and other structures such as the inferior vena cava (IVC).
- Whether there is sufficient tissue available to save (the tumor is not too big and the blood supply to the remaining adrenal tissue can be preserved).
- Whether the surgeon has enough experience with this more technically challenging operation. Few surgeons perform adrenal-sparing operations regularly.
What is the Purpose of Adrenal-Sparing Surgery?
Adrenal-sparing (partial) adrenalectomy allows the adrenal tumor or tumors to be removed while preserving unaffected adrenal tissue, with the goal of preventing adrenal insufficiency. This is especially important in patients with tumors in both adrenal glands. In PA and AHC the tumors are almost always benign and often small, and disease in both glands is common, which makes these conditions well suited to adrenal-sparing surgery. In selected patients with metastases to both adrenal glands (cancers that started somewhere else, such as the lung, kidney, colon or melanoma, and spread to the adrenal glands) it may also be considered.Can an Adrenal-Sparing Adrenalectomy be Performed via Mini Back Scope Adrenalectomy (MBSA)?
Read more about partial adrenal surgery on our adrenal surgery blog
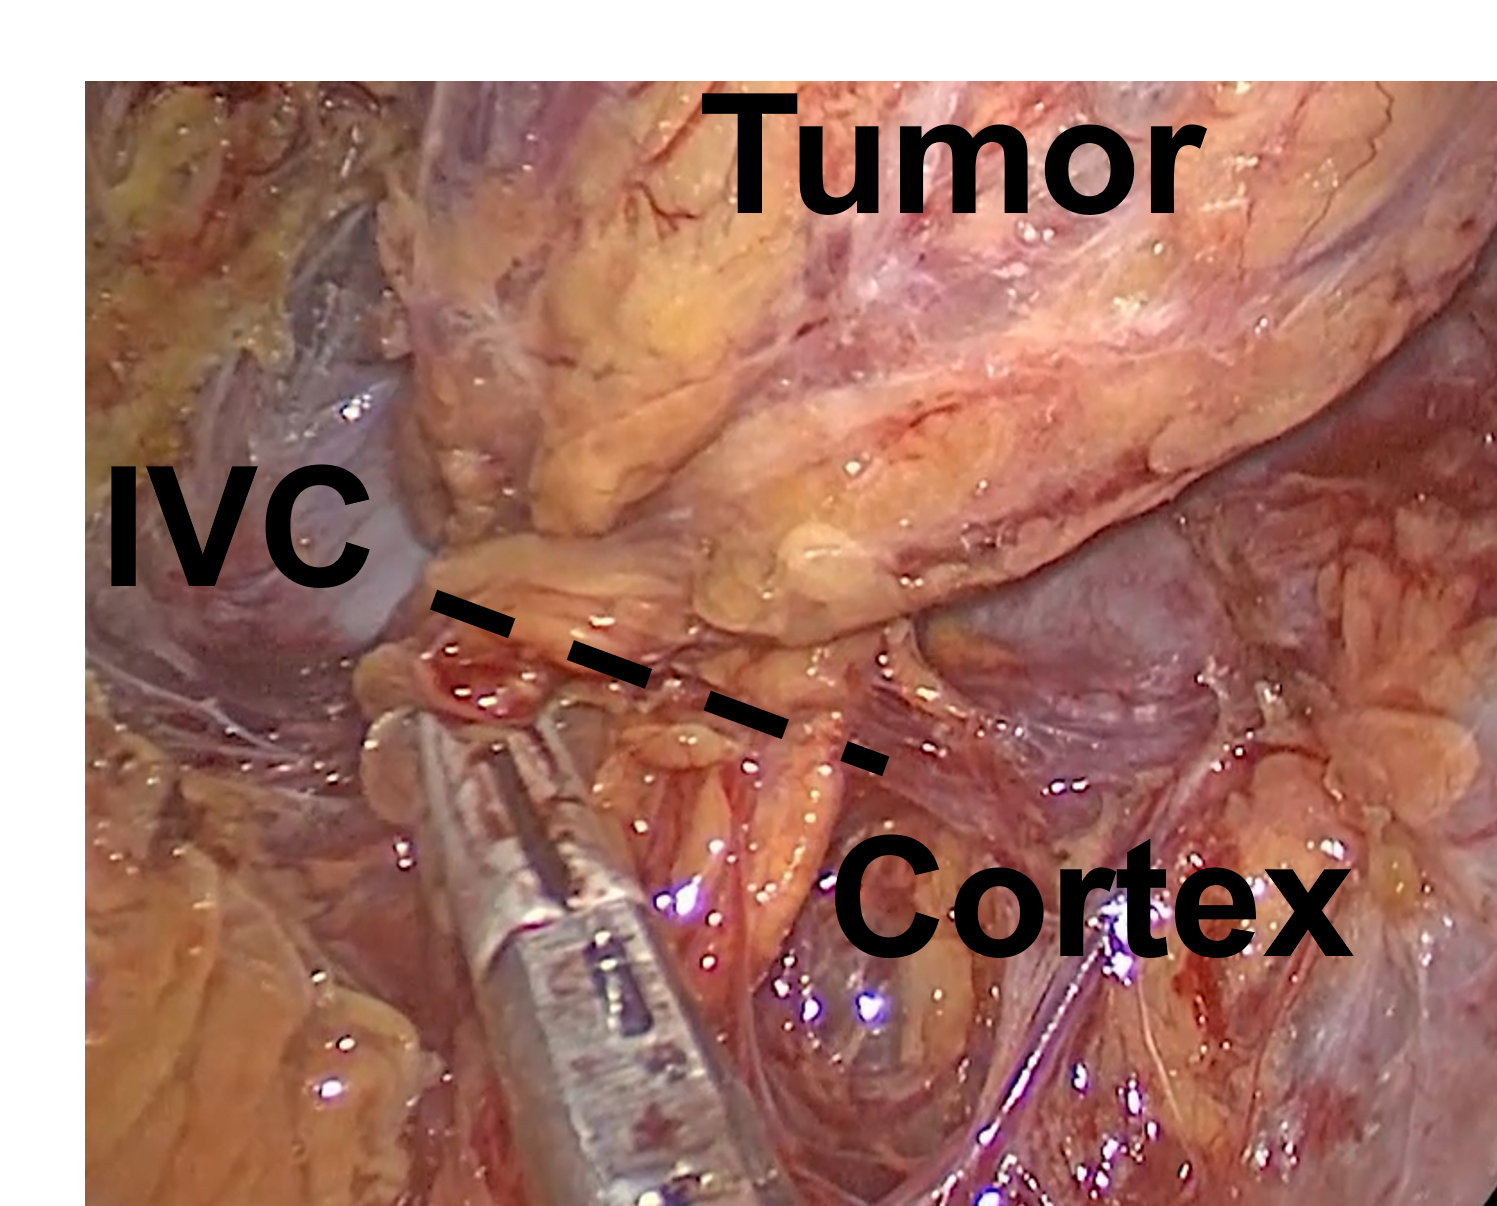 Adrenal-Sparing (Partial) Adrenalectomy Performed via Right Mini Back Scope Adrenalectomy (MBSA). The tissue is divided at the dotted line, removing the tumor, but preserving the normal adrenal tissue and the inferior vena cava (IVC).
Absolutely, in experienced hands. The Mini Back Scope Adrenalectomy (MBSA) is particularly well suited to adrenal-sparing surgery, and in our view better suited than laparoscopic transabdominal adrenalectomy (LTA), robotic or open (through the abdomen) adrenal surgery. The MBSA is ideal for patients with bilateral disease (disease in both the right and the left adrenal glands), because both glands can be reached without repositioning the patient. It can be used, for instance, in patients with bilateral pheochromocytomas in the setting of multiple endocrine neoplasia 2A (MEN2A) or von Hippel-Lindau (VHL) syndrome, and in patients who have had previous adrenal surgery. You can watch a video of Dr. Carling performing an adrenal-sparing adrenalectomy via the MBSA here.
Adrenal-sparing adrenalectomy is an invaluable option for patients with genetic syndromes associated with pheochromocytomas. These syndromes include MEN2, VHL, and neurofibromatosis type 1 (NF1), as well as others. About half of people with MEN2A and up to a quarter of those with VHL develop a pheochromocytoma, and in many of them it eventually affects both glands. In these syndromes the tumors usually have a low risk of spreading (metastasizing). Adrenal-sparing adrenalectomy removes the affected tissue while leaving behind enough tissue to prevent adrenal insufficiency. The honest trade-off is that any adrenal tissue left behind can grow a new tumor: in the largest international registry of patients with bilateral, mostly hereditary pheochromocytoma, a tumor recurred in the remnant in about 13%, typically many years later, and was treated with a further operation. Survival was no worse than after removal of both whole glands. That is why lifelong annual follow-up with metanephrine testing is essential. Read more about pheochromocytoma genetics.
Who is a Good Candidate For a Partial Adrenal Operation?
Most patients who are thought to be good candidates for adrenal-sparing adrenalectomy based on preoperative imaging will be able to undergo it. The same four factors determine whether it can be done:- The type of tumor.
- The size of the tumor and its relationship to the adrenal vein and other structures.
- Whether enough healthy tissue, with its blood supply, can be saved.
- The surgeon's experience with this operation.
What About Patients Who Need Surgery on Both Adrenal Glands (Bilateral Adrenalectomy)?
When adrenal-sparing surgery is performed for tumors in both adrenal glands, most patients do not require lifelong steroid replacement (hydrocortisone, prednisone, etc.). But not every patient ends up steroid-free: in large international series, roughly three-quarters do. Even with an adequate remnant, the remaining tissue may be "asleep" for a while after surgery, so some patients need steroids temporarily, and a few permanently. We test cortisol the morning after surgery to see who needs replacement. In many patients with bilateral tumors, we remove the entire adrenal gland on one side and perform a partial resection on the other side. For bilateral PA and AHC we usually stage the two operations at least 6 weeks apart: the first operation often does more good than expected, the pathology guides what the other side needs, and the remaining gland has time to recover. This has to be individualized for each patient. The key to preventing adrenal insufficiency is to save at least about 30% of one gland with its blood supply.Watch a video of Dr. Carling performing an adrenal-sparing (partial) adrenalectomy.
Last updated October 2026.