How is Primary Aldosteronism (Conn's Syndrome) Diagnosed?
A number of tests help establish the diagnosis of PA, but primarily we want to know whether too much aldosterone is being produced by one or both of the adrenal glands, since over-production of aldosterone is the cause of this disease. The diagnosis of primary aldosteronism (Conn's syndrome) follows a logical three-step approach:- Screening for the disease. This is done with blood tests for aldosterone, renin and potassium. The 2025 Endocrine Society guideline recommends screening everyone with high blood pressure.
- Confirming the disease. The blood tests are repeated. Additional confirmatory testing is needed only in selected patients.
- Finding the source. A CT scan of the adrenal glands and, in selected patients, adrenal vein sampling show whether one or both glands are responsible.
Lab Testing for the Diagnosis of Primary Aldosteronism (Conn's Syndrome)
The ARR Screening Test. The aldosterone-to-renin ratio (ARR) is the most reliable screening test for primary aldosteronism. It is very easy to do and only requires one tube of blood to be drawn from your arm. Ask your doctor for a simple blood test to check your plasma aldosterone concentration (PAC) and your renin (plasma renin activity, PRA). Classically, patients with primary aldosteronism have: Plasma aldosterone concentration (PAC) = HIGH (or in the upper normal range), and Plasma renin activity (PRA) = LOWDividing the PAC by the PRA gives the aldosterone-to-renin ratio (ARR). If the renin is low and the ARR is greater than 20, the patient may well have primary aldosteronism. Look at the renin first: the aldosterone level is often within the normal range, and what matters is that it is too high for a renin that is switched off. Some of these patients also have a low blood potassium level (hypokalemia), but most have a normal potassium level. A blood potassium level is a common blood test performed as part of a routine annual physical exam. Ask your doctor to go back and see whether your potassium level has ever been low. Of course, if you must take potassium supplements, then you are hypokalemic (you have low blood potassium). Low potassium has other causes too (for example, diuretics such as Lasix, or vomiting and diarrhea), but unexplained low potassium together with high blood pressure should always prompt testing for PA.
Blood pressure medications that can interfere with testing for primary aldosteronism.- Spironolactone (Aldactone): can cause a false-negative result
- Eplerenone (Inspra): can cause a false-negative result
- Amiloride: can cause a false-negative result
- Diuretics (Lasix, etc): can cause a false-negative result
- ACE inhibitors (Lisinopril, Captopril, etc): can cause a false-negative result
- Angiotensin receptor blockers, ARBs (Losartan, etc): can cause a false-negative result
- Beta-blockers (Metoprolol, etc): can cause a false-positive result
- Clonidine: can cause a false-positive result
A false-negative result says that you do NOT have PA when you really do; a false-positive result says that you DO have it when you really do not. Spironolactone, eplerenone, amiloride, diuretics, ACE inhibitors and ARBs raise renin and can hide the disease. Beta-blockers and clonidine lower renin and can make the ratio look abnormal when it is not. But it is better to test aldosterone and renin while on blood pressure medications than never to have your levels checked at all. A renin that stays low even though you take a drug that should raise it is in fact strong evidence for PA. Never stop any of these medications without talking specifically about it with your doctor.
Should Blood Pressure Drugs be Stopped Before Aldosterone and Renin Testing?
Not necessarily. The first screening test can be done while you are taking your usual medications. If the result is unclear, your doctor may repeat it after stopping the interfering drugs: about 4 weeks for spironolactone, eplerenone, amiloride and other diuretics, and about 2 weeks for ACE inhibitors, ARBs, beta-blockers and clonidine. Important! In many patients this is not feasible, because the blood pressure will go too high.The most important medications to be off during testing are spironolactone (Aldactone), eplerenone (Inspra) and amiloride. If your doctor says it is not safe for you to stop your blood pressure medications for a few weeks, it is still better to have your testing done while on medications than not to be screened at all.
Testing in the morning. The ARR test is most sensitive and most accurate when samples are collected in the morning after patients have been out of bed for at least 2 hours, usually after they have been seated for 5–15 minutes. A low potassium level should be corrected before testing, because low potassium lowers aldosterone and can hide the disease. Because aldosterone levels go up and down during the day and the test can be affected by medications, a single unimpressive result should not close the case; the test may have to be repeated (a couple of weeks apart).
For many doctors, diagnosing primary aldosteronism is hard, time-consuming and sometimes confusing (the exceptions being endocrinologists who focus on endocrine hypertension and kidney doctors, nephrologists, with a focus on secondary hypertension). If you or your doctor want to run the laboratory tests by us, please do! We are here to help. Send us your laboratory results, including what medications you were on during the testing.
In addition to evaluating the ARR, it is important to review the absolute aldosterone value: the higher the plasma aldosterone concentration (PAC), the more severe the disease, and a PAC above 20 ng/dl with low potassium indicates severe PA. The renin level should also be considered on its own. A very low (suppressed) renin together with an aldosterone that is not low is the hallmark of primary aldosteronism. A low renin alone does not prove it, because some people with ordinary high blood pressure also have a low renin. Importantly, laboratories need to report individual values for both aldosterone and renin, as well as the ARR.
Check cortisol too. Between 13% and 27% of patients with PA also make too much cortisol, a combination we call PA+AHC (adrenal hypercortisolism). Every patient with PA should therefore have a 1-mg overnight dexamethasone suppression test. A morning cortisol above 1.8 µg/dL after the tablet is abnormal, and it can change which operation is best for you.
Classic Cases of Primary Aldosteronism (High Aldosterone, Low Renin)
Are you an "ALDO slam dunk"? Do you have classic primary aldosteronism? So, to make things easier, let us start with a textbook, classic patient with primary aldosteronism. Are you an ALDO slam dunk? As you have read so far, arriving at an accurate diagnosis of PA can be a bit tricky. However, this is familiar ground for us. We evaluate patients with possible primary aldosteronism every day. Textbook cases are what we call ALDO slam dunks. These are patients in whom the diagnosis is clear from the first set of labs. Many of our patients with PA are ALDO slam dunks. These are some of the characteristics of an ALDO slam dunk.The Classic Patient with Primary Aldosteronism (Conn's Syndrome). The "ALDO Slam Dunk"
- High blood pressure (relatively short duration)
- Tend to be female
- Tend to be younger
- Low blood potassium (hypokalemia)
- No other risk factors for high blood pressure (smoking, obesity, kidney disease, diabetes, etc)
- High plasma aldosterone concentration (PAC), often above 20 ng/dl
- Low (suppressed) plasma renin activity (PRA)
- Hypertension responding well to Spironolactone (or similar drugs)
- May have symptoms (frequent urination, muscle cramps, fatigue, etc.)
If you are an ALDO slam dunk, in a way, congratulations. (Note, we do not take it lightly that you have a disease, but this is fixable!). You do not need any more confirmatory testing. You can move straight to an adrenal-protocol CT scan (if you cannot have intravenous contrast, a CT without contrast or an adrenal-protocol MRI can be used). If the CT is of high quality and shows an unequivocal tumor in one adrenal gland and a completely normal gland on the other side, you can often skip adrenal vein sampling as well and move straight to what will likely be a curative adrenalectomy. Read about the operation, the Mini Back Scope Adrenalectomy (MBSA)
Almost all patients who are accurately diagnosed with one-sided (unilateral) PA benefit from surgery, but women and younger patients tend to benefit the most. The operation cures the aldosterone excess in the large majority and lowers your risk of future strokes, heart attacks, arrhythmias (for instance, atrial fibrillation) and premature death. Read more about surgery for primary aldosteronism.
Note for our international patients: Aldosterone and renin may be reported in conventional units (ng/dl and ng/ml/h) or in SI (Systeme International) units (for example, pmol/l), and many laboratories now measure direct renin concentration instead of plasma renin activity. The cut-off for the ARR depends on the units used. Do not worry about this. We are used to evaluating laboratory data from around the world and can easily make sense of it. It is helpful, though, to include the reference range of each assay from the laboratory when you send us your data.
Confirmatory Tests for Primary Aldosteronism: Who Needs Them?
Some patients are not an ALDO slam dunk and will need a more detailed work-up. This is where the confirmatory tests come in. They are needed only selectively: many patients with clearly positive screening tests can skip them.The first confirmatory test you should have is a repeat of the aldosterone-to-renin ratio (ARR), as it is the most reliable screening test for primary aldosteronism. Again, this is easy. Ask your doctor for a simple blood test to check your plasma aldosterone concentration (PAC) and plasma renin activity (PRA). In our practice, two sets of blood tests that both show a normal-to-high aldosterone with a low renin are generally enough to move on to a CT scan.
Borderline Cases... Not Quite Sure? The 2025 Endocrine Society guideline no longer recommends a confirmatory (aldosterone suppression) test for everyone. It suggests one only for patients whose screening results are borderline (equivocal), to confirm or exclude the diagnosis of primary aldosteronism. One of the issues is that the experts have had difficulty agreeing on the ideal confirmatory test.
The following (somewhat cumbersome) tests are used for this purpose. We rarely find them necessary:
- Oral sodium loading test
- Intravenous saline loading test
- Fludrocortisone suppression test
- Captopril challenge test
It's Time To Get A Scan!
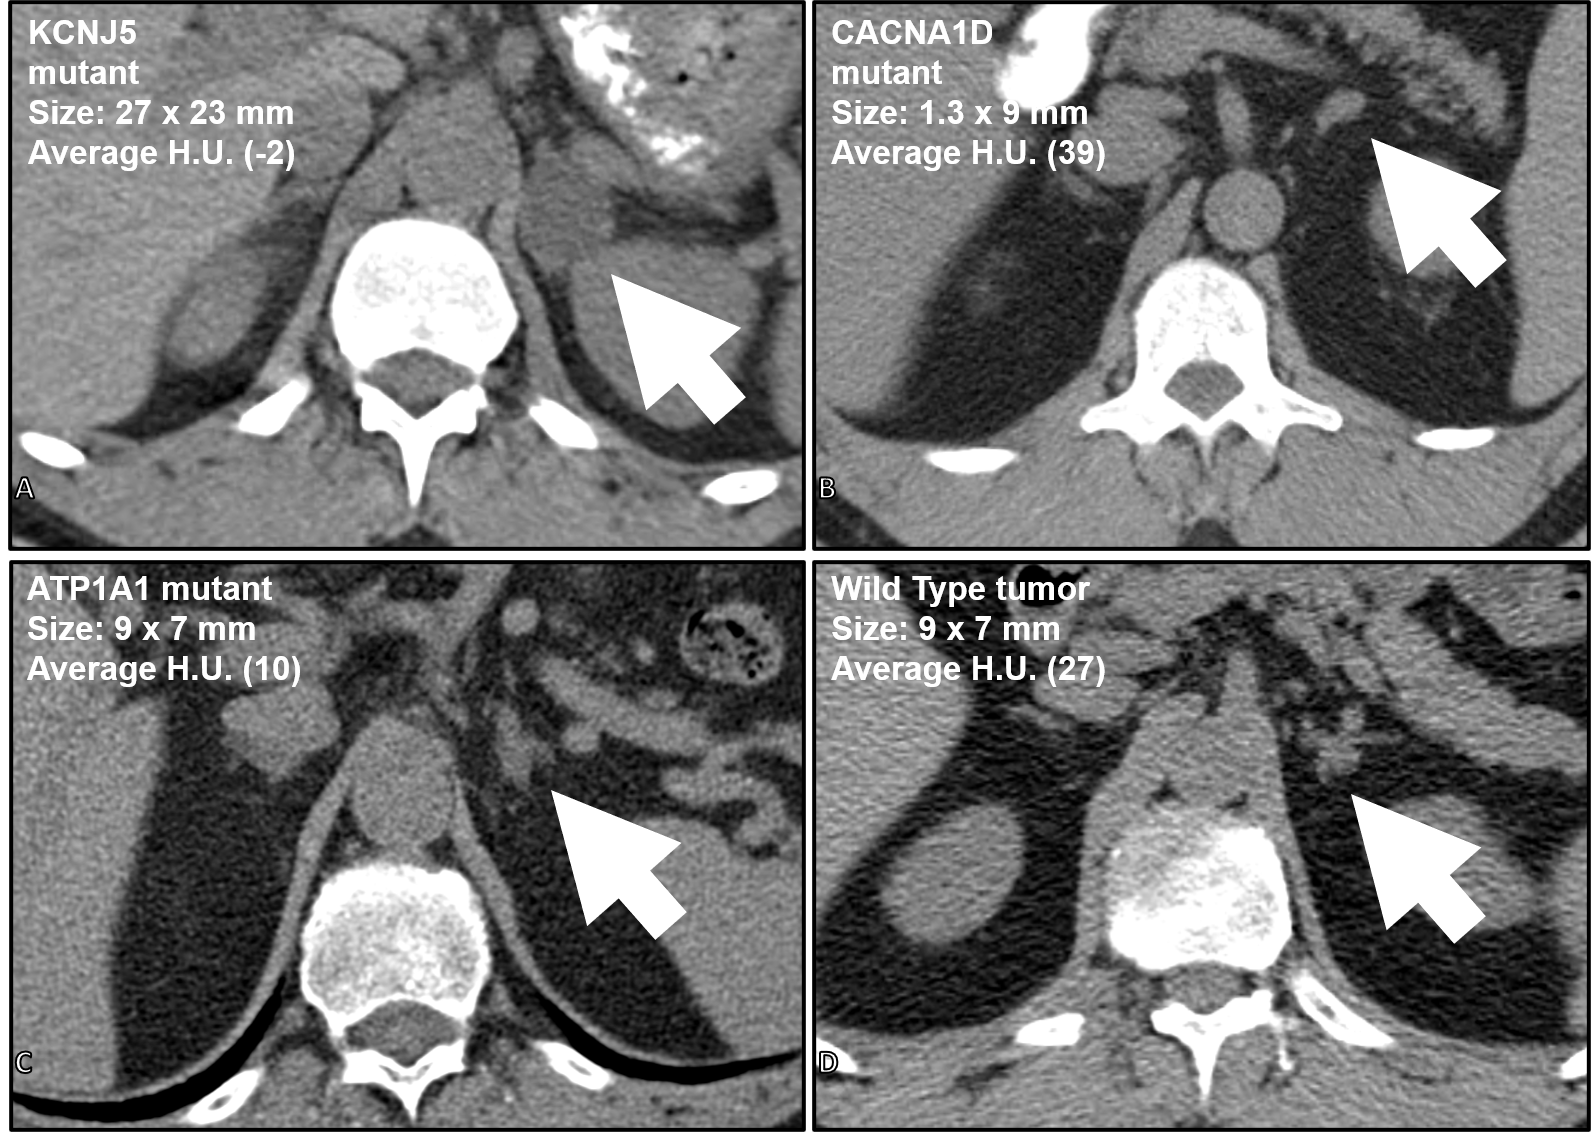 CT scans from 4 different patients, all with a left aldosterone-producing tumor (arrows) causing primary aldosteronism. Based on the severity of the disease, the patient's characteristics and the CT scan appearance, we can advise whether the patient can go straight to surgery or needs adrenal vein sampling.
Once the blood tests have established the diagnosis of primary aldosteronism, you may move ahead to the next step: adrenal imaging with an adrenal-protocol CT scan (if you cannot have intravenous contrast, a CT without contrast or an adrenal-protocol MRI can be used). We have an entire section of this website on scans for adrenal tumors. Bottom line, there really is one first scan to get: an adrenal-protocol CT scan. Most people with adrenal tumors need only one scan. Read about adrenal scans and about CT scans for primary aldosteronism.
Keep in mind that a CT scan shows the shape of the adrenal glands, not which cells are making aldosterone; a harmless nodule can mislead. Even so, in many cases Dr. Carling can tell where the excess aldosterone is coming from by combining the CT scan with the laboratory results. He has published on this topic. Based on the severity of the disease, the patient's characteristics and the findings on a high-quality CT scan, we can advise which patients can go straight to surgery and which ones need more studies (i.e. adrenal vein sampling).
What is Adrenal Vein Sampling and Do I Need It?
Maybe, but many patients do not. Adrenal vein sampling (AVS) is the standard test to distinguish one-sided (unilateral) from two-sided (bilateral) sources of aldosterone. It is an interventional radiology study: through small catheters, blood samples are obtained from each adrenal vein and from the inferior vena cava. AVS is invasive and technically difficult, and it carries a 0.2-2.5% risk of a major complication, so we use it selectively, when the result would change the plan:- Severe PA with an unequivocal tumor in one gland on a high-quality CT and a completely normal opposite gland: these patients can often go straight to surgery without AVS.
- Mild PA: this often involves both glands and responds well to medication (spironolactone or eplerenone), so neither AVS nor surgery is usually needed.
- Moderate or severe PA with a CT scan that is negative or ambiguous: this is where AVS has its greatest value, because it can identify patients who would otherwise be denied a curative operation.
- Tumors in both glands: AVS can help when only a one-sided total adrenalectomy is planned.
Read more on our adrenal vein sampling (AVS) page and on our adrenal surgery blog
Note from the Carling Adrenal Center: Unless your endocrinologist has extensive experience in identifying an expert interventional radiologist to perform adrenal vein sampling (if you need it), call us. We can help you find a team that does this procedure safely and with a high success rate. The advantage of AVS is that it shows whether the excess aldosterone comes from just one adrenal gland, and whether it is the right or the left.
Again, if you have primary aldosteronism, let us review your imaging (send us your CT scan). Dr. Carling has reviewed the CT scans of thousands of patients with adrenal tumors and has published research on primary aldosteronism. Also, do not waste time obtaining unnecessary, expensive scans (for instance, an MRI, which few patients with this type of adrenal problem need) or an invasive adrenal vein sampling procedure before we have looked at your results. Sometimes you need it, but often you do not. We can usually tell quickly what is going on and what the next step should be.
Last updated October 2026.